Cagrilintide is a lab-made, long-lasting copy of amylin, a hormone tied to feeling full. It has been tested in human trials as a once-weekly shot for appetite and body weight, alone and with semaglutide. No regulator has approved it.
In brief
- It switches on amylin receptors for a long time. That hormone pathway is separate from the one GLP-1 drugs use and works alongside it. A fatty acid attached to the molecule keeps it in the blood long enough for one dose a week.
- It was tested alone in a phase 2 dose-finding trial in adults with overweight or obesity. It has been tested far more with semaglutide, as "CagriSema", in phase 1b to phase 3 trials in people with obesity or type 2 diabetes.
- Scientists have looked at its effects on appetite, blood sugar control and markers such as blood pressure, in a sub-study and in pooled analyses. Much of a phase 3 program on the pairing (REDEFINE and REIMAGINE) has been reported.
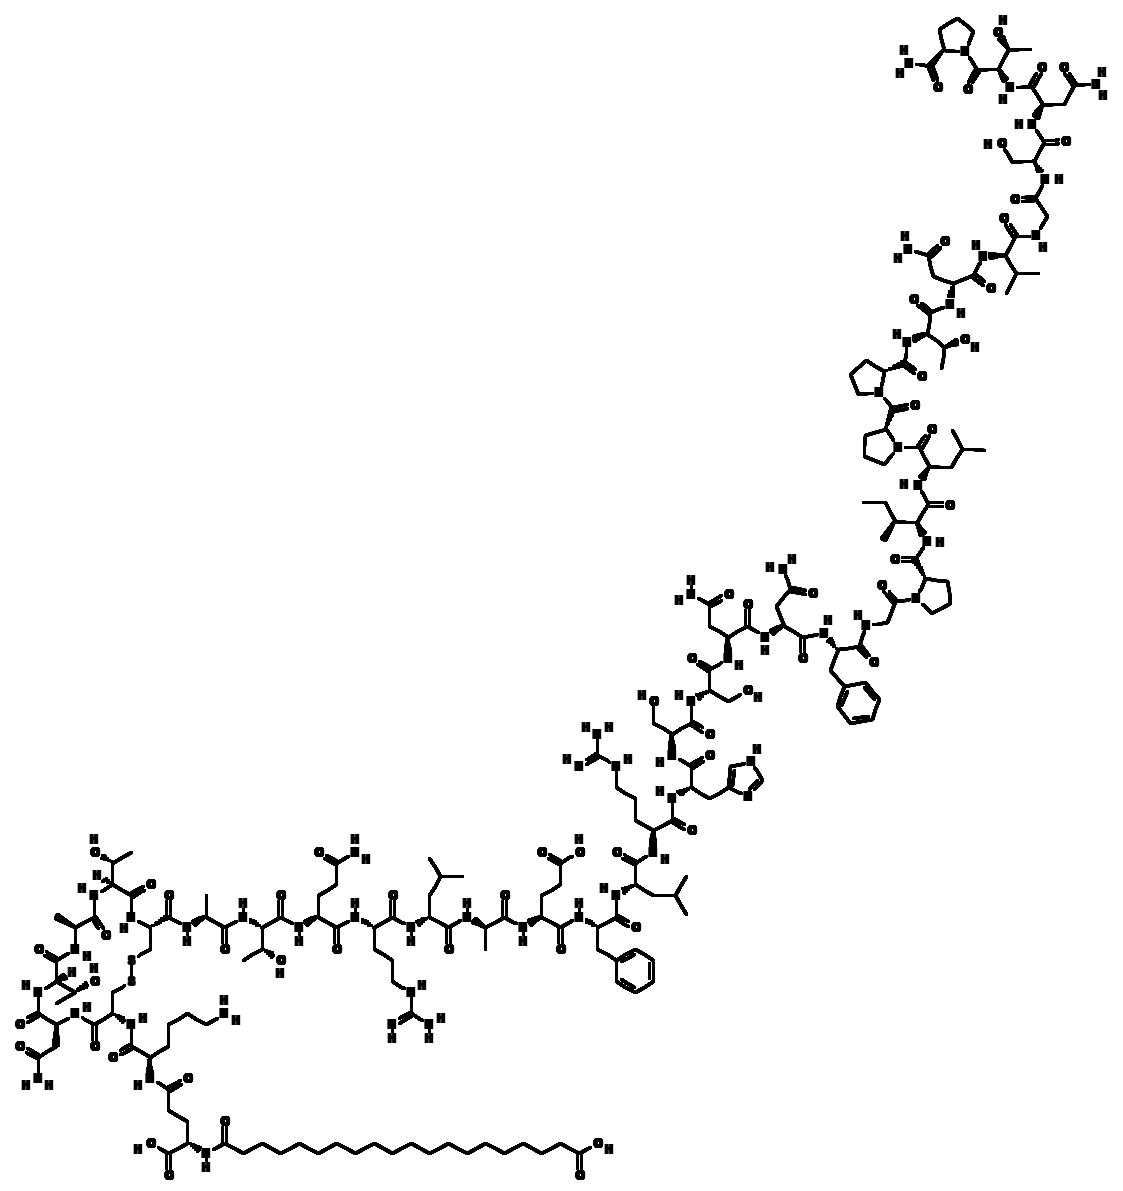
What cagrilintide is
Cagrilintide is a lab-made peptide that has been tested in people. The trials were randomized and controlled, and ran from phase 1b to phase 3. The people in them were adults with obesity, overweight or type 2 diabetes. Its one stand-alone trial was phase 2. The phase 3 trials test it with a second drug, semaglutide. Some of them include a group that got cagrilintide alone. As of 2026, it is not approved for medical use in people anywhere in the world, alone or in that pairing. That includes the FDA, the EMA in Europe and the MHRA in the UK.
A peptide is a short chain of amino acids, the building blocks of protein. Cagrilintide is a long-acting analog, or altered copy, of human amylin. Amylin is a hormone made of 37 amino acids, also called islet amyloid polypeptide. Beta cells in the pancreas normally release it together with insulin.
In the trials run so far, cagrilintide was given once a week as a shot under the skin.
It is not a GLP-1 drug. Drugs like semaglutide target the GLP-1 receptor. This one is built to switch on amylin receptors. That is a separate hormone pathway that works alongside GLP-1, and researchers have tied it to feeling full and to control of how much is eaten [7]. Scientists have tested it alone. They have tested it far more with semaglutide, a drug that switches on the GLP-1 receptor. The research name for that pairing is “CagriSema” [9].
It was not the first amylin analog tried in people. Pramlintide came earlier. It acts for a shorter time and needs several shots a day. Earlier research tested pramlintide for its effect on blood sugar in people with diabetes who were already using insulin. That made amylin analogs a drug class of their own, well before this once-a-week design came along [3].
A 2021 paper gave the first full account of how the drug is built [10]. The trials that followed include two phase 3 programs meant to support approval. REDEFINE covers obesity and REIMAGINE covers type 2 diabetes. Much of both has now been reported [15], [17].
Everything in this guide comes from published, peer-reviewed trial data or from lab research on how the drug acts. It is here for research and learning only.
How much research there is
Human trials up to phase 3, all paid for by the company that makes the compound. Most of the late-stage data is for the pairing with semaglutide.
| Question | Answer |
|---|---|
| Stage of the evidence | Phase 3 for the CagriSema pairing (the REDEFINE and REIMAGINE programs), with much of it reported [15], [17]. For cagrilintide alone, one phase 2 trial [11], plus single groups inside two phase 3 trials of the pairing [15], [17] |
| Kinds of studies | Randomized, double-blind human trials from phase 1b to phase 3, with placebo and active drug comparisons. Lab and receptor studies back these up |
| Who was tested | Adults with obesity or overweight. Adults who have type 2 diabetes |
| Checked by others | Results held up across separate groups of people: the trials of cagrilintide alone, the phase 1b and phase 2 pairing trials, and the phase 3 trials. An outside team also pooled three of the trials in a systematic review with a meta-analysis [16]. That is a second look at the maker’s data, not a new trial |
| Who paid for the trials | Every published trial comes from the program sponsored by the maker of the compound. Academic groups outside the company have only reanalyzed or pooled that same trial data |
| Longest study | 68 weeks, in the REDEFINE 1 and REIMAGINE 2 phase 3 trials [15], [17] |
| Approval | Still under study. Not approved by the FDA, the EMA or the MHRA, alone or as CagriSema |
| Do the results agree | Yes. Alone, higher doses gave larger effects. As CagriSema, the signals for blood sugar and weight change were steady in both the type 2 diabetes and the obesity groups |
How it might work
Amylin is a hormone, and it has receptors of its own. They are not the GLP-1 receptor that drugs like semaglutide target. Researchers think this split is the very reason the two fit together. Switching on amylin receptors would add to a GLP-1 drug, not repeat it [4].
Amylin receptors
Amylin was first pulled out of human pancreas tissue and described in 1987. It was found to be released along with insulin, with a signaling job of its own [1].
Amylin does not use one receptor made just for it. A receptor is the spot on a cell where a hormone attaches. Amylin and its analogs switch on what drug scientists call “amylin receptors”. Each one is a complex, made when the receptor for calcitonin joins with one of several helper proteins called RAMPs (receptor activity-modifying proteins). Basic molecular pharmacology research described this setup in detail [4].
Cagrilintide is built to switch on this complex. It is meant to act for far longer than natural amylin or the older amylin analogs in the research record [7].
Appetite and fullness
Scientists have studied amylin receptors and eating in animals for decades.
- Early rodent research found that giving amylin cut food intake. This did not depend on the metabolic actions of insulin [2].
- Later work found a link between amylin signaling and leptin sensitivity. Leptin is another hormone. In models of diet-induced obesity, switching on amylin receptors helped bring back the response to leptin [5].
- Wider reviews point to two proposed causes of the fullness results. One is signaling in the area postrema. This part of the brainstem lacks a complete blood-brain barrier. The other is slower emptying of the stomach [6], [7].
Why pair it with a GLP-1 drug
Amylin receptors and the GLP-1 receptor are thought to use separate pathways that do not overlap. Their proposed effects on appetite fit together. So researchers formed a hypothesis: using both in one study could lower body weight more than either pathway alone. The same reasoning shows up across the incretin research field, where one molecule or one mixed product is built to hit more than one target [8]. Incretins are gut hormones such as GLP-1.
This hypothesis is the basis of the CagriSema program. In it, cagrilintide has been given alongside semaglutide in trials at phases 1b, 2 and 3 [9], [13].
How the molecule is built
Like other long-acting peptide analogs in this field, it starts from a changed amylin backbone. A fatty acid part is attached to it. That part helps the molecule bind to albumin, a protein in blood. The binding stretches its half-life, the time it takes for half of it to leave the bloodstream. The half-life becomes long enough to support one shot under the skin each week. The first chemistry paper on the drug, a medicinal chemistry report, lays out this design in detail [10].
Amylin analogs differ in how they balance binding across receptors. Animal research has compared it with KBP-336. That is another compound that acts on both amylin and calcitonin receptors. It looked at how that balance relates to metabolic effects [12].
What the studies found
These are the main published human results, for cagrilintide alone and for CagriSema. All are phase 1b to phase 3 trials. The maker of the compound ran or sponsored every one.
Cagrilintide alone, phase 2
- This dose-finding trial enrolled 706 adults who had obesity or overweight. It was randomized and double-blind. It had a placebo group and an active drug group, on daily liraglutide, to compare against. It tested five once-weekly doses, from 0.3 mg to 4.5 mg, for 26 weeks. Body weight fell more at higher doses. The average drop ran from 6.0% at the lowest dose to 10.8% at the highest. It was 3.0% with placebo and 9.0% with liraglutide [11].
- The side effects reported most often were in the gut: nausea, diarrhea and constipation. They were mostly described as mild to moderate, and they clustered in the weeks when the dose was being raised. That fits what is known about how people tolerate amylin and incretin drugs as a class [11].
Safety of the pairing, phase 1b
- A randomized, controlled phase 1b trial gave several doses of cagrilintide together with semaglutide. It measured safety, how well people tolerated the drugs, how the body handled them, and how they acted on the body. People tolerated the pair about as well as each drug studied alone. The two drugs did not change how the body handled each other in any unexpected way [9].
Type 2 diabetes
- Phase 2. This trial was randomized and double-blind. It lasted 32 weeks and enrolled 92 adults who had type 2 diabetes. They got both drugs together, semaglutide alone or cagrilintide alone, each once a week. HbA1c, a measure of blood sugar, fell by 2.2 percentage points with the pairing, 1.8 with semaglutide and 0.9 with cagrilintide. Body weight fell by 15.6%, 5.1% and 8.1% [13]. An editorial that ran with it looked at how research ties obesity to type 2 diabetes [14].
- Phase 3, REIMAGINE 2. This later trial enrolled 2,713 adults who had type 2 diabetes and ran for 68 weeks. It compared the pairing with semaglutide by itself, cagrilintide by itself and placebo. At the 2.4 mg dose, HbA1c fell by 1.91 percentage points with the pairing and by 1.75 with semaglutide alone [17]. An editorial set those results inside the wider body of research on treating type 2 diabetes [18].
Heart and metabolic markers
- Blood pressure. REDEFINE 1 is part of the phase 3 obesity program. It ran for 68 weeks in 3,417 adults who had obesity or overweight. An analysis of it looked just at blood pressure. Systolic pressure, the top number, fell by 10.9 mm Hg with the pairing and by 2.8 with placebo [15].
- Pooled data. A meta-analysis, built on a systematic review, pooled three trials with 3,545 people. People on the pairing lost about 7.5 percentage points more weight than people on semaglutide alone. Weight loss with cagrilintide alone was close to that with semaglutide [16].
Safety
In human trials
- Gut problems were the side effects seen most often in trials of the drug alone and of the pairing. These were nausea, diarrhea and constipation. They were mostly mild to moderate and most common while the dose was being raised [11], [9], [13].
- A pooled analysis of three trials found that side effects overall, and serious ones, were about as common with the pairing as with semaglutide alone. Nausea and reactions at the injection site were more common with the pairing. Serious side effects were more common with cagrilintide alone than with semaglutide [16].
- Blood pressure changes seen with CagriSema so far have moved in a good direction. They have not raised safety concerns [15].
What is not known
- Peer-reviewed research has not yet shown long-term safety past the treatment lengths of the phase 1b to phase 3 trials in print.
- Safety and effect have not been shown in groups the trials left out. Examples are teenagers, pregnancy, and people with serious liver or kidney problems.
- This guide’s review of the published research found no formal drug interaction studies, other than its use together with semaglutide.
- Work not paid for by the maker is still limited.
- Published data on mechanism have not yet fully separated how much of the CagriSema effect in people comes from the amylin receptors and how much from the GLP-1 receptor.
Legal status in the US
- Not FDA approved. Cagrilintide has no approval for any medical use from the FDA, alone or as CagriSema. The same is true of the EMA in Europe and the MHRA in the UK.
- Banned in sport. It is a peptide hormone that switches on a receptor. That class of compound falls under class S2 of the World Anti-Doping Agency Prohibited List (peptide hormones, growth factors, related substances and mimetics). S2 substances are banned at all times, both in competition and out of it.
- Research use. Suppliers provide it strictly for use in laboratory research.
Limits of the research
- Phase 3 data is mostly about the pairing. Most published phase 3 evidence is for CagriSema, which is cagrilintide plus semaglutide. For the drug alone, there is one phase 2 trial, plus single groups inside phase 3 trials of the pairing.
- The maker paid for the trials. All the primary trial data found for this guide come from the research program sponsored by the maker of the compound. No independent academic trial has been published yet.
- Little long-term data. Treatment lengths in the peer-reviewed record do not reach continuous use over several years. Nobody yet knows the longer-term effects or how well people tolerate it.
- The cause is not fully pinned down. Lab research supports how amylin receptors work. Sorting out the exact human share of the amylin receptors from the GLP-1 share inside CagriSema is still an open question.
- Narrow groups. Trials so far enrolled only adults with obesity, overweight or type 2 diabetes. The results should not be stretched to other groups or settings.
- Possible bias in what gets published. This cannot be ruled out. It applies to any drug research that comes mainly from trials that the developer designed and reported.
Human trials show weight loss with cagrilintide. The strongest data is for its pairing with semaglutide, and its maker paid for every trial.
References
Selected peer-reviewed references, each verified against the CrossRef API before inclusion. Ordered by date of publication.
- Cooper G, Willis A, Clark A, Turner R, et al. (1987). Purification and characterization of a peptide from amyloid-rich pancreases of type 2 diabetic patients. Proceedings of the National Academy of Sciences, 84(23), 8628–8632. DOI: 10.1073/pnas.84.23.8628
- Morley J, Flood J (1991). Amylin decreases food intake in mice. Peptides, 12(4), 865–869. DOI: 10.1016/0196-9781(91)90148-I
- Thompson R, Pearson L, Schoenfeld S, Kolterman O, et al. (1998). Pramlintide, a Synthetic Analog of Human Amylin, Improves the Metabolic Profile of Patients With Type 2 Diabetes Using Insulin. Diabetes Care, 21(6), 987–993. DOI: 10.2337/diacare.21.6.987
- Hay D, Christopoulos G, Christopoulos A, Poyner D, et al. (2005). Pharmacological Discrimination of Calcitonin Receptor: Receptor Activity-Modifying Protein Complexes. Molecular Pharmacology, 67(5), 1655–1665. DOI: 10.1124/mol.104.008615
- Roth J, Roland B, Cole R, Trevaskis J, et al. (2008). Leptin responsiveness restored by amylin agonism in diet-induced obesity: Evidence from nonclinical and clinical studies. Proceedings of the National Academy of Sciences, 105(20), 7257–7262. DOI: 10.1073/pnas.0706473105
- Lutz T (2011). Effects of Amylin on Eating and Adiposity. In Handbook of Experimental Pharmacology: Appetite Control, 231–250. DOI: 10.1007/978-3-642-24716-3_10
- Hay D, Chen S, Lutz T, Parkes D, et al. (2015). Amylin: Pharmacology, Physiology, and Clinical Potential. Pharmacological Reviews, 67(3), 564–600. DOI: 10.1124/pr.115.010629
- Boyle C, Lutz T, Le Foll C (2018). Amylin – Its role in the homeostatic and hedonic control of eating and recent developments of amylin analogs to treat obesity. Molecular Metabolism, 8, 203–210. DOI: 10.1016/j.molmet.2017.11.009
- Enebo L, Berthelsen K, Kankam M, Lund M, et al. (2021). Safety, tolerability, pharmacokinetics, and pharmacodynamics of concomitant administration of multiple doses of cagrilintide with semaglutide 2·4 mg for weight management: a randomised, controlled, phase 1b trial. The Lancet, 397(10286), 1736–1748. DOI: 10.1016/S0140-6736(21)00845-X
- Kruse T, Hansen J, Dahl K, Schäffer L, et al. (2021). Development of Cagrilintide, a Long-Acting Amylin Analogue. Journal of Medicinal Chemistry, 64(15), 11183–11194. DOI: 10.1021/acs.jmedchem.1c00565
- Lau D, Erichsen L, Francisco A, Satylganova A, et al. (2021). Once-weekly cagrilintide for weight management in people with overweight and obesity: a multicentre, randomised, double-blind, placebo-controlled and active-controlled, dose-finding phase 2 trial. The Lancet, 398(10317), 2160–2172. DOI: 10.1016/S0140-6736(21)01751-7
- Larsen A, Mohamed K, Sonne N, Bredtoft E, et al. (2022). Does receptor balance matter? – Comparing the efficacies of the dual amylin and calcitonin receptor agonists cagrilintide and KBP-336 on metabolic parameters in preclinical models. Biomedicine & Pharmacotherapy, 156, 113842. DOI: 10.1016/j.biopha.2022.113842
- Frias J, Deenadayalan S, Erichsen L, Knop F, et al. (2023). Efficacy and safety of co-administered once-weekly cagrilintide 2·4 mg with once-weekly semaglutide 2·4 mg in type 2 diabetes: a multicentre, randomised, double-blind, active-controlled, phase 2 trial. The Lancet, 402(10403), 720–730. DOI: 10.1016/S0140-6736(23)01163-7
- Apovian C, McDonnell M (2023). CagriSema and the link between obesity and type 2 diabetes. The Lancet, 402(10403), 671–673. DOI: 10.1016/S0140-6736(23)01291-6
- Verma S, Böttcher M, Brown P, Dicker D, et al. (2026). CagriSema Reduces Blood Pressure in Adults With Overweight or Obesity: REDEFINE 1. Hypertension, 83(2). DOI: 10.1161/HYPERTENSIONAHA.125.26055
- Ahmed M, Hassan M, Tahir M, Hussain M, et al. (2026). Efficacy and Safety of Cagrilintide and Cagrisema Versus Semaglutide as Anti-Obesity Medications: A Systematic Review, Meta-Analysis and Meta-Regression. Diabetes, Obesity and Metabolism, 28(6), 4828–4836. DOI: 10.1111/dom.70667
- Buse J, Bajaj H, Dalskov S, Donaldson L, et al. (2026). Cagrilintide–semaglutide (CagriSema) versus semaglutide or cagrilintide in people with type 2 diabetes (REIMAGINE 2): a double-blind, randomised, controlled, phase 3 study. The Lancet Diabetes & Endocrinology, 14(8), 662–677. DOI: 10.1016/S2213-8587(26)00125-7
- Scheen A (2026). Cagrilintide–semaglutide: a new option for patients with type 2 diabetes. The Lancet Diabetes & Endocrinology, 14(8), 621–624. DOI: 10.1016/S2213-8587(26)00129-4
Related compounds
- Retatrutide: One peptide that switches on GLP-1, GIP and glucagon receptors, tested for weight and blood sugar.
- MOTS-c: Small peptide made from a mitochondrial gene, tested in mice for blood sugar and muscle effects.