Thymosin alpha-1 is a chain of 28 amino acids that the body makes, mostly in the thymus. A lab-made copy, Zadaxin, is an approved drug in more than 30 countries for hepatitis and weak immune systems. The FDA has not approved it.
In brief
- It switches on the TLR9 and TLR2 sensors on dendritic cells, which helps T cells mature and shifts the balance between Th1 and Th2 responses.
- Some countries, including Italy, China, Russia and parts of Southeast Asia, approve it as an add-on for long-term hepatitis B and C, but the US and UK do not.
- Its human safety record is among the largest for any peptide drug, built over decades of regulated medical use and several Phase II and III randomized trials.
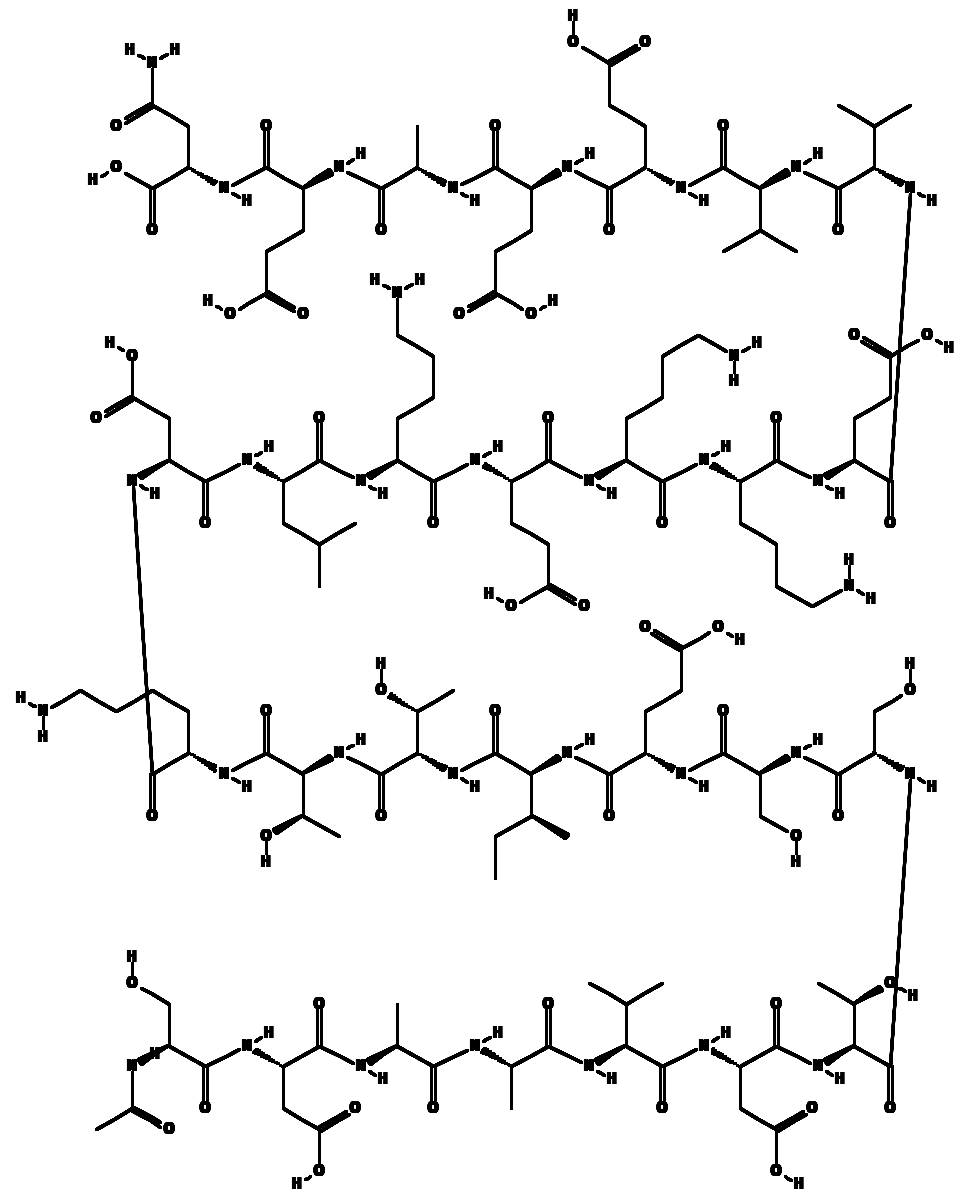
What Thymosin Alpha-1 is
Thymosin Alpha-1 is an immune peptide that has been tested in people far more than most. Several hundred thousand patients have received it over several decades. Randomized trials have tested it in hepatitis, sepsis, cancer and HIV. The largest one enrolled 1,106 adults. A lab-made copy is an approved drug in more than 30 countries. The FDA has not approved it in the US, and the MHRA has not approved it in the UK.
A peptide is a chain of amino acids, the building blocks of protein. This one has 28, with an acetyl group capping one end. The order is Ac-SDAAVDTSSEITTKDLKEKKEVVEEAEN. It is also written Tα1 or Tα-1, and its drug name is thymalfasin.
The body makes Tα1 by cutting it out of a larger protein called prothymosin alpha. Most of that happens in the lining cells of the thymus, an organ of the immune system. It has also been found in the spleen, the liver and other lymph tissue. Allan Goldstein and colleagues first pulled it from cow thymus in the 1970s. Among the thymus compounds that change how the immune system responds, it is one of the best described 1, 2.
The drug version is an exact lab-made copy of the natural peptide. SciClone Pharmaceuticals and its regional partners sell it as Zadaxin. China, Italy, Russia, the Philippines, Vietnam and several other Southeast Asian countries are among those that have approved it. The approved uses span long-term hepatitis B, long-term hepatitis C, immune deficiency that is inborn or acquired, melanoma, and boosting vaccines in patients on kidney dialysis 3, 4.
In the US, the FDA has given it orphan drug status for three diseases. They are malignant melanoma, hepatitis B and hepatitis C. That is not the same as approval.
Because so many patients have received it, the human safety record is very large for a peptide. This guide sums up published work on how Tα1 acts, what trials found, and where regulators stand. It is for education only. It is not medical advice, and it does not endorse human use outside approved countries and regulated medical care.
How much research there is
Tα1 stands apart from most research peptides. It is an approved drug in many countries, with many human trials behind it.
| Question | Answer |
|---|---|
| Grade of evidence | Approved pharmaceutical derivative. Sold in 30+ countries as Zadaxin (thymalfasin) |
| Published studies | Several hundred in total. 25+ are cited here as examples |
| Kinds of human studies | Several Phase II and III randomized trials in hepatitis B, hepatitis C, sepsis and melanoma. Also a large body of observational and registry data |
| People studied | Tens of thousands enrolled in randomized trials. Hundreds of thousands more treated through approved use |
| Largest trial | TESTS, in sepsis, with 1,106 patients (BMJ 2025) |
| Where it is approved | China, Italy, Russia, Indonesia, Malaysia, the Philippines, Singapore, Taiwan, Vietnam and others, 30+ in all |
| US | No FDA approval. Orphan drug status from the FDA for melanoma and for hepatitis B and C |
| UK | No MHRA approval. It is an unlicensed medicine there |
| Sport | Absent from the WADA 2025 Prohibited List |
| Doses used in trials | Most often 1.6 mg under the skin, from twice a week to twice a day. Some trials used other doses. The schedule changes with the disease |
How it might work
Tα1 does many things at once. It does not act like a drug with one target. It behaves more like one of the body’s own regulators. It acts on the sensors of the first-line immune system. Through them, it reaches the slower, targeted immune response. It resets how dendritic cells are programmed and how T cells develop. The result depends on the state of inflammation 2, 5.
Dendritic cells are immune cells that show pieces of germs to T cells. T cells are white blood cells that direct and carry out attacks.
The TLR9 sensor
Toll-like receptor 9 (TLR9) is the clearest target found so far. It is a sensor inside immune cells that spots a kind of DNA, called unmethylated CpG DNA.
Romani, Bistoni, Puccetti and colleagues tested Tα1 in mice. It switched on a signal chain that runs from TLR9 through MyD88 to IRF7. This happened in two kinds of mouse dendritic cells, conventional and plasmacytoid. The cells made type I interferons, which are antiviral alarm signals. The treated mice were protected from invasive aspergillosis, a fungal infection, and from cytomegalovirus 5, 6.
Later lab work suggests that Tα1 does not grip TLR9 tightly itself. It seems to boost the CpG signal inside the cell. That fits a helper role, like the boosters added to vaccines.
The TLR2 sensor
A second sensor, Toll-like receptor 2 (TLR2), also carries the Tα1 signal. This happens mainly on macrophages, the cells that swallow germs, and on myeloid dendritic cells.
The TLR2 signal passes through the MyD88 link and ends by switching on NF-κB, a master control for immune genes. The cell then makes IL-10, a calming signal, and IDO, an enzyme whose full name is indoleamine 2,3-dioxygenase. Together these push the immune system toward tolerance. That helps explain a puzzle. Tα1 can strengthen defense against germs and calm excess inflammation at once 2, 7.
Acting on TLR2 and TLR9 together seems to account for much of what doctors have seen in sepsis and viral infection.
Helping T cells mature
The oldest finding is that Tα1 brought back T cell growth in animals with no thymus or a weak immune system.
- It raises the surface markers CD3, CD4 and CD8 on T cells.
- It increases the output of the thymus.
- It lifts CD4+ T cell counts in the blood when lymphocytes, a type of white blood cell, are low. That includes immune damage from chemotherapy, HIV and severe viral illness 8, 9.
In severe COVID-19, patients given Tα1 showed a reversal of T cell exhaustion. Two exhaustion markers, PD-1 and Tim-3, went down. This reflects the same support for T cell growth 10.
The balance of Th1 and Th2
Th1 and Th2 are two styles of T cell response. In long-term viral infection, Tα1 tilts the balance toward Th1. It raises three signals: interferon-gamma (IFN-γ), interleukin-2 (IL-2) and IL-12. It holds down excess IL-4 and IL-6.
This tilt is thought to be why some hepatitis B and hepatitis C patients kept the virus down for a long time when Tα1 was added to interferon treatment 11, 12.
In sepsis, where inflammation runs out of control, the same routes seem to work the other way. Tα1 restores IFN-γ and brings back HLA-DR, a marker that monocytes, a kind of white blood cell, had lost.
Natural killer cells
Natural killer (NK) cells destroy tumor cells and cells infected with a virus. Tα1 raised their killing power in healthy volunteers and in patients with weak immune systems. Tests on cells taken from the body showed NK cells breaking open more of both kinds of target 2, 13.
Two causes have been proposed. Dendritic cells switched on by Tα1 make more IL-12. Tα1 also acts directly on the receptors that set NK cells off. This priming of NK cells is one reason given for adding Tα1 to treatment in trials for melanoma and for hepatocellular carcinoma, a liver cancer.
Dendritic cells
Dendritic cells are the hub of what Tα1 does. It makes both plasmacytoid and myeloid dendritic cells mature. They carry more MHC class II, more CD80 and CD86, and more CCR7. With these, they are better at showing germ pieces to T cells and at traveling to lymph nodes 5, 7.
Tα1 also helps macrophages grown from monocytes swallow more germs, using complement receptors. And it raises their output of reactive oxygen species, germ-killing chemicals, in a controlled way that does not cause harm 14.
Taken together, Tα1 looks less like a drug aimed at one receptor and more like a conductor that links the fast and slow arms of the immune system.
What the studies found
Few peptide drugs have this much published human data. Across the approved uses, the number of people treated is put in the hundreds of thousands. These are the trials that mattered most.
Hepatitis B
Several randomized trials tested Tα1 for long-term hepatitis B virus (HBV) infection, both alone and with interferon-alpha.
- Tα1 alone. An early randomized trial by Andreone and colleagues found that Tα1 by itself gave a virus response on par with standard interferon. Patients tolerated it much better 15.
- With antiviral pills. Later pooled analyses of randomized trials in Asian patients looked at Tα1 added to nucleos(t)ide analogs, a class of antiviral drugs. More patients cleared HBV DNA, and more showed HBeAg seroconversion, a blood marker tracked in hepatitis B. Reviews by Sjogren and by Ciancio and Rizzetto summed up thymalfasin use in hepatitis B 11, 16.
Italy, China and many Southeast Asian countries have approved the drug for long-term hepatitis B.
Hepatitis C
For hepatitis C virus (HCV), the randomized results were more mixed.
- Patients who had failed earlier treatment. Ciancio and colleagues ran a Phase III trial at many centers. They added Tα1 to pegylated interferon-alfa-2a and ribavirin. Early virus response improved a little. Sustained response, meaning the virus stays undetectable after treatment ends, was not significantly better than with standard care 17.
- Patients never treated before. Camerini, Ciancio and colleagues had tested the same mix before that. The way virus levels fell over time looked more promising 18.
Newer drugs called direct-acting antivirals (DAAs) now cure most HCV without Tα1, so drug development has moved on. The HCV trials are still a rich source of data on safety and on how Tα1 acts.
Cancer, as an add-on
Tα1 has been tested as an add-on in several cancers.
- Malignant melanoma. Rasi, Garaci and colleagues ran an open-label Phase II trial in advanced melanoma. They gave Tα1 and low-dose interferon-alpha after the chemotherapy drug dacarbazine. A later review counts it among the early trials that reported tumor responses 19, 20.
- Hepatocellular carcinoma (HCC). Case series and small trials tested Tα1 after trans-arterial chemoembolization, a treatment that blocks a tumor’s blood supply and delivers chemotherapy. Others paired it with the drug sorafenib. There were signs that the immune system rebuilt better. Survival results varied from study to study 20.
The data for Tα1 used alone in cancer are much weaker than the add-on data. It is not treated as a main cancer drug.
Sepsis
Sepsis is now one of the most active research areas for Tα1.
- ETASS (Wu J and colleagues, Critical Care 2013) was a single-blind randomized trial at many centers. It enrolled 361 patients with severe sepsis. Deaths from any cause within 28 days were 35.0% in the control group, against 26.0% with Tα1. On the main measure, that gap was not statistically significant 21.
- TESTS (Wu J and colleagues, BMJ 2025) was much larger. It was a Phase 3, double-blind trial at many centers with 1,106 adults with sepsis. It is the best current evidence on Tα1 in critical care 22.
COVID-19 in intensive care
In the first waves of the pandemic, several hospitals in China reported using Tα1 in very sick patients.
The study cited most often appeared in Clinical Infectious Diseases. Its authors were Liu, Pan, Hu and colleagues. They looked back at the records of 76 patients with severe COVID-19. Among those given Tα1, 11.1% died, against 30.0% of the others. Their lymphocyte counts recovered. The CD8+ T cell exhaustion markers PD-1 and Tim-3 reversed 10.
Later analyses and pooled reviews broadly backed a sign of benefit in severe COVID-19 with low lymphocytes. All of them were observational or not randomized. No forward-looking Phase III trial was finished before the pandemic eased.
Rebuilding immunity: HIV, vaccines and older adults
- HIV. Tα1 was tested on top of antiretroviral therapy. Chadwick and colleagues ran a pilot randomized trial. Patients tolerated it well, but it added only a modest extra gain in CD4+ T cells beyond what the HIV drug combination (HAART) achieved 24. A broad review by Matteucci and colleagues sums up the HIV evidence and the reasoning behind it 25.
- Vaccines. Other studies found that more dialysis patients responded to the hepatitis B vaccine when given Tα1, and that older adults responded better to the flu vaccine. Several countries approved it as a vaccine booster on that basis 3. In a pilot study by Carraro and colleagues, dialysis patients given Tα1 responded better to a pandemic H1N1 flu vaccine 23.
Safety
For a peptide drug, Tα1 has an unusually well described safety record. It comes from randomized trials in long-term hepatitis, sepsis, HIV and cancer, and from decades of approved use in Italy, China and elsewhere. Reports have steadily described it as well tolerated 3, 4, 21.
- Most common side effects: mild, short-lived reactions where the shot went in, such as redness and local soreness, in a minority of patients.
- Whole-body effects: rare reports of a brief low fever, tiredness or muscle aches. These usually came in the first weeks and seldom limited the dose.
- Lab tests: large trials showed no steady pattern of harm to the blood, liver or kidneys.
- Serious side effects: controlled trials showed no sign of more serious events than placebo. That includes the TESTS sepsis trial with 1,106 patients 22.
- Drug interactions: none that mattered clinically were found when it was combined with standard antibiotics, antiretrovirals, ribavirin or interferons.
- Who is ruled out: the approved label lists people allergic to the drug. In some countries it also lists transplant patients on immune-suppressing drugs. In theory, a restored immune system could reject the graft.
No sign of serious harm across a very large number of patients is not an endorsement of use outside the clinic. The safety data come from regulated medical care using pharmaceutical-grade product. They do not come from research-grade material given without medical supervision.
Legal status in the US
- Not FDA approved. Thymosin Alpha-1 is not cleared for marketing in the US. It has orphan drug status from the FDA for malignant melanoma and for long-term hepatitis B and C. No new drug application (NDA) has won full approval.
- Approved in other countries. Thymalfasin (Zadaxin) is authorized in Italy for long-term hepatitis B, as an add-on for long-term hepatitis C, and as an immune regulator in people with weak immune systems. In all, regulators in more than 30 countries, including China, Russia and much of Southeast Asia, have approved it. Their approved uses are hepatitis B, hepatitis C, immune deficiency and boosting hepatitis B vaccination in dialysis patients. The MHRA in the UK has not licensed it.
- Sport. Thymosin Alpha-1 is not on the WADA 2025 Prohibited List. Thymosin Beta-4 (TB-500), a different peptide, is banned by name. The list is updated every year, so this can change.
- Research use. Suppliers sell it for in vitro laboratory research, labeled “not for human use”.
Limits of the research
- Trials differ a lot. The randomized trials used different doses and schedules (most often 1.6 mg, from twice a week to twice a day) and lengths (2 weeks to 12 months). Patient groups and main measures differed too. That makes pooling them hard.
- Weak data for Tα1 alone in cancer. It is rarely used as a tumor-killing drug by itself. Where it was tested alone in cancer, responses were uncommon.
- Mixed hepatitis C results. The key combination trials did not all show a better sustained response than interferon plus ribavirin alone. Direct-acting antivirals have largely replaced immune-based treatment.
- Cost is debated. Several health technology reviews, mostly in European systems that decide what to pay for, have questioned whether Tα1 adds enough benefit at its current price compared with other treatments.
- COVID-19 data mostly look backward. The most cited studies are observational or from a single center. They are not forward-looking randomized trials, so the apparent survival benefit needs caution.
- Approval is patchy. Approval in 30+ countries is not approval by the FDA, the MHRA or the EMA. Research-grade lab-made peptide might also differ biologically from the pharmaceutical product sold where it is approved.
- Many routes at once. Tα1 acts on several pathways together. That makes it hard to tie a clinical result to one receptor or route, and it complicates drug development built around biomarkers.
Thymosin Alpha-1 has one of the largest sets of human data of any peptide drug and is approved in many countries. Trial results are still mixed, and the FDA has not approved it.
References
Selected peer-reviewed references. Not exhaustive. All citations DOI-verified via PubMed where indicated.
- Garaci E, Pica F, Sinibaldi-Vallebona P, et al. Thymosin alpha(1) in combination with cytokines and chemotherapy for the treatment of cancer. Int Immunopharmacol. 2003;3(8):1145-1150. DOI: 10.1016/S1567-5769(03)00053-5. PMID: 12860169.
- Romani L, Bistoni F, Montagnoli C, et al. Thymosin alpha1: an endogenous regulator of inflammation, immunity, and tolerance. Ann N Y Acad Sci. 2007;1112:326-338. DOI: 10.1196/annals.1415.002. PMID: 17495242.
- King R, Tuthill C. Immune modulation with thymosin alpha 1 treatment. Vitam Horm. 2016;102:151-178. DOI: 10.1016/bs.vh.2016.04.003. PMID: 27450734.
- Camerini R, Garaci E. Historical review of thymosin alpha 1 in infectious diseases. Expert Opin Biol Ther. 2015;15 Suppl 1:S117-S127. DOI: 10.1517/14712598.2015.1033393. PMID: 26098768.
- Bozza S, Gaziano R, Bonifazi P, et al. Thymosin alpha1 activates the TLR9/MyD88/IRF7-dependent murine cytomegalovirus sensing for induction of anti-viral responses in vivo. Int Immunol. 2007;19(11):1261-1270. DOI: 10.1093/intimm/dxm097. PMID: 17804687.
- Romani L, Bistoni F, Gaziano R, et al. Thymosin alpha 1 activates dendritic cells for antifungal Th1 resistance through toll-like receptor signaling. Blood. 2004;103(11):4232-4239. DOI: 10.1182/blood-2003-11-4036. PMID: 14982877.
- Serafino A, Pierimarchi P, Pica F, et al. Thymosin α1 as a stimulatory agent of innate cell-mediated immune response. Ann N Y Acad Sci. 2012;1270:13-20. DOI: 10.1111/j.1749-6632.2012.06707.x. PMID: 23050812.
- Goldstein AL, Badamchian M. Thymosins: chemistry and biological properties in health and disease. Expert Opin Biol Ther. 2004;4(4):559-573. DOI: 10.1517/14712598.4.4.559. PMID: 15102606.
- Garaci E, Favalli C, Pica F, et al. Thymosin alpha 1: from bench to bedside. Ann N Y Acad Sci. 2007;1112:225-234. DOI: 10.1196/annals.1415.044. PMID: 17600290.
- Liu Y, Pan Y, Hu Z, et al. Thymosin alpha 1 reduces the mortality of severe coronavirus disease 2019 by restoration of lymphocytopenia and reversion of exhausted T cells. Clin Infect Dis. 2020;71(16):2150-2157. DOI: 10.1093/cid/ciaa630. PMID: 32442287.
- Sjogren MH, Rodrigues-Arenas S. Thymalfasin: an immune system enhancer for the treatment of liver disease. J Gastroenterol Hepatol. 2004;19(12 Suppl):S69-S72. DOI: 10.1111/j.1440-1746.2004.03635.x. PMID: 15546253.
- Garaci E, Pica F, Serafino A, et al. Thymosin α1 and cancer: action on immune effector and tumor target cells. Ann N Y Acad Sci. 2012;1269:26-33. DOI: 10.1111/j.1749-6632.2012.06697.x. PMID: 23045965.
- Garaci E, Pica F, Mastino A, et al. Historical review on thymosin alpha1 in oncology: preclinical and clinical experiences. Expert Opin Biol Ther. 2015;15 Suppl 1:S31-S39. DOI: 10.1517/14712598.2015.1017466. PMID: 26096345.
- Serafino A, Pica F, Andreola F, et al. Thymosin α1 activates complement receptor-mediated phagocytosis in human monocyte-derived macrophages. J Innate Immun. 2014;6(1):72-88. DOI: 10.1159/000351587. PMID: 23797159.
- Andreone P, Cursaro C, Gramenzi A, et al. A randomized controlled trial of thymosin-alpha1 versus interferon alfa treatment in patients with hepatitis B e antigen antibody- and hepatitis B virus DNA-positive chronic hepatitis B. Hepatology. 1996;24(4):774-777. DOI: 10.1002/hep.510240404. PMID: 8855175.
- Ciancio A, Rizzetto M. Thymalfasin in the treatment of hepatitis B and C. Ann N Y Acad Sci. 2010;1194:141-146. DOI: 10.1111/j.1749-6632.2010.05487.x. PMID: 20536462.
- Ciancio A, Andreone P, Kaiser S, et al. Thymosin alpha-1 with peginterferon alfa-2a/ribavirin for chronic hepatitis C not responsive to IFN/ribavirin: an adjuvant role? J Viral Hepat. 2012;19(Suppl 1):52-59. DOI: 10.1111/j.1365-2893.2011.01524.x. PMID: 22233415.
- Camerini R, Ciancio A, De Rosa A, Rizzetto M. Studies of therapy with thymosin alpha1 in combination with pegylated interferon alpha2a and ribavirin in individuals chronically infected with hepatitis C virus. Ann N Y Acad Sci. 2007;1112:368-374. DOI: 10.1196/annals.1415.047. PMID: 17600286.
- Rasi G, Terzoli E, Izzo F, et al. Combined treatment with thymosin-alpha1 and low dose interferon-alpha after dacarbazine in advanced melanoma. Melanoma Res. 2000;10(2):189-192. DOI: 10.1097/00008390-200010020-00012. PMID: 10803720.
- Costantini C, Bellet MM, Pariano M, et al. A reappraisal of thymosin alpha1 in cancer therapy. Front Oncol. 2019;9:873. DOI: 10.3389/fonc.2019.00873. PMID: 31555601.
- Wu J, Zhou L, Liu J, et al. The efficacy of thymosin alpha 1 for severe sepsis (ETASS): a multicenter, single-blind, randomized and controlled trial. Crit Care. 2013;17(1):R8. DOI: 10.1186/cc11932. PMID: 23327199.
- Wu J, Pei F, Zhou L, et al. The efficacy and safety of thymosin alpha1 for sepsis (TESTS): multicentre, double-blinded, randomised, placebo-controlled, phase 3 trial. BMJ. 2025;388:e082583. DOI: 10.1136/bmj-2024-082583. PMID: 39814420.
- Carraro G, Naso A, Montomoli E, et al. Thymosin-alpha 1 (Zadaxin) enhances the immunogenicity of an adjuvated pandemic H1N1v influenza vaccine (Focetria) in hemodialyzed patients: a pilot study. Vaccine. 2012;30(6):1170-1180. DOI: 10.1016/j.vaccine.2011.12.014. PMID: 22178096.
- Chadwick D, Pido-Lopez J, Pires A, et al. A pilot study of the safety and efficacy of thymosin alpha 1 in augmenting immune reconstitution in HIV-infected patients with low CD4 counts taking highly active antiretroviral therapy. Clin Exp Immunol. 2003;134(3):477-481. DOI: 10.1111/j.1365-2249.2003.02331.x. PMID: 14632754.
- Matteucci C, Grelli S, Balestrieri E, et al. Thymosin alpha 1 and HIV-1: recent advances and future perspectives. Future Microbiol. 2017;12:141-155. DOI: 10.2217/fmb-2016-0125. PMID: 28106477.
- Pica F, Gaziano R, Casalinuovo IA, et al. Serum thymosin alpha 1 levels in normal male subjects. Clin Ter. 2018;169(6):e230-e233. DOI: 10.7417/CT.2018.2085. PMID: 30488926.
- Tuthill C, Rios I, McBeath R. Thymosin alpha 1: past clinical experience and future promise. Ann N Y Acad Sci. 2010;1194:130-135. DOI: 10.1111/j.1749-6632.2010.05482.x. PMID: 20536460.
Related compounds
- TB-500: Lab-made piece of Thymosin Beta-4, tested mostly in animals for cell movement and wound healing.
- BPC-157: Lab-made chain of 15 amino acids, tested in animals for blood vessel growth and tissue repair.
- Selank: Lab-made chain of seven amino acids, approved in Russia as a nasal spray for anxiety.