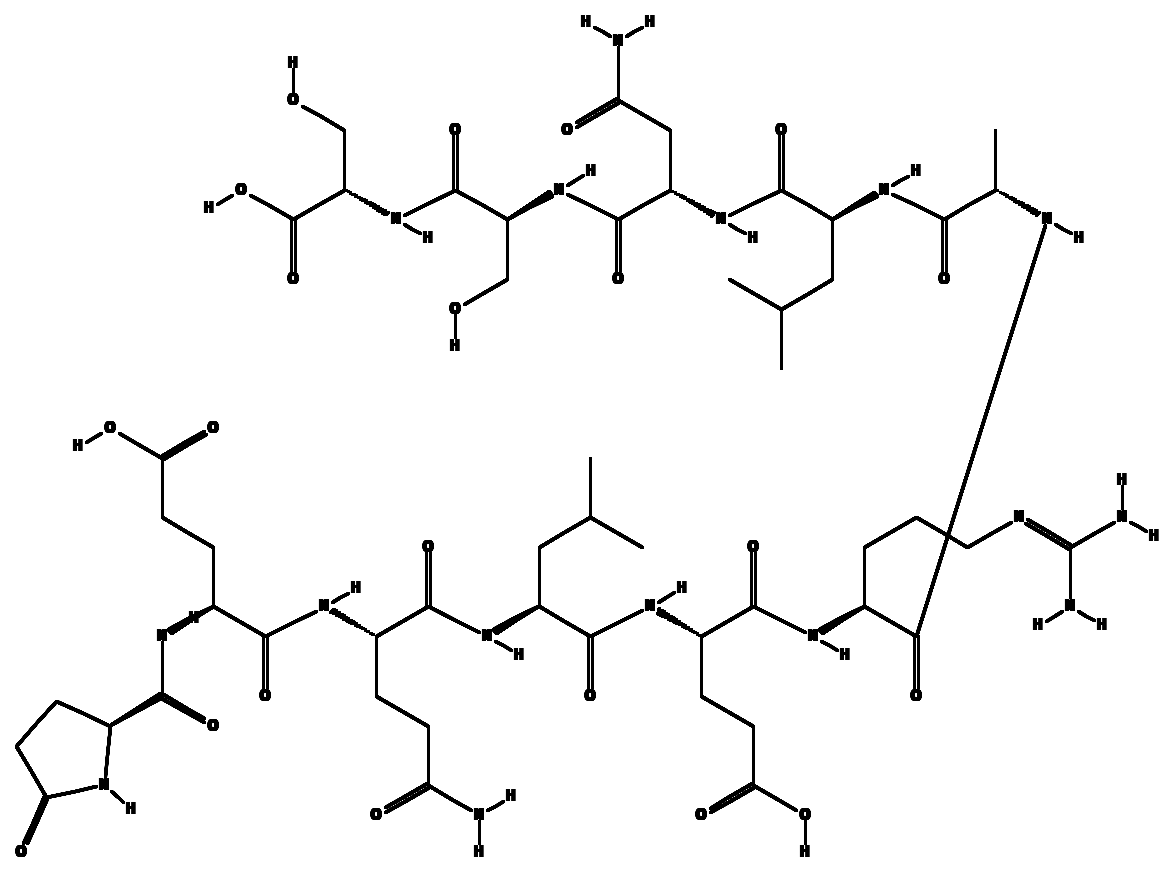
ARA-290, also called cibinetide, is a chain of 11 amino acids copied from part of the hormone EPO. It was built to protect tissue without raising red blood cells. It has been tested in small Phase 2 trials for nerve damage, and in animals.
In brief
- It is copied from the hormone EPO but does not bind the classic paired EPO receptor, and research models have not shown it to raise red blood cell production the way EPO does, which is the reason it was designed.
- It is tested for picking out a receptor pair called the innate repair receptor (IRR), made of the EPO receptor and the beta-common receptor (CD131), which animal and cell studies report on tissue that is injured or under metabolic stress, not healthy tissue.
- First developed by Araim Pharmaceuticals, it is tested in small fiber and diabetic nerve damage, with nerve fiber counts in the cornea and skin, in nerve damage linked to sarcoidosis, and in wider work on cell protection and calming inflammation.
What ARA-290 is
ARA-290 is a lab-made peptide that has been tested in people, but only in small Phase 2 trials. Phase 2 is the middle stage of drug testing. As of 2026, those trials covered two groups of adults. One group had nerve damage linked to a disease called sarcoidosis. The other had type 2 diabetes with nerve symptoms. The trials cited in this guide compared the peptide with a placebo [12], [15], [18]. No Phase 3 results were found for this guide. The compound is not approved to treat anything in people.
A peptide is a short chain of amino acids, the building blocks of protein. ARA-290 has 11. Its research name is cibinetide.
The chain is copied from a hormone called erythropoietin, or EPO. EPO is known for telling the body to make red blood cells. The 11 amino acids come from a part of the folded hormone called helix B, which sits on its outer surface [3].
EPO also protects tissue. Scientists showed that this second job could be split from the blood cell job, both in structure and in function. A family of engineered peptides came out of that work, and ARA-290 is one of them [1].
The whole point of ARA-290 is that it is non-erythropoietic. That means it does not drive red blood cell production. It does not bind the classic EPO receptor that controls red cell output. In the studies reviewed here, nobody reported that it raised red cell production. Research suggests it picks out a different receptor group tied to tissue repair and cell protection.
Araim Pharmaceuticals first developed ARA-290. The company’s patent filings describe this class of EPO-based peptides that protect tissue without making blood cells [6].
This guide sums up the peer-reviewed research for education and lab research. For laboratory research use only. Not for human consumption.
How much research there is
A handful of small human trials, mostly by one circle of scientists, plus a wide base of animal and cell studies.
| Question | Answer |
|---|---|
| Stage | Phase 2. The trials cited here had a placebo group. They covered small fiber neuropathy linked to sarcoidosis, and nerve damage in type 2 diabetes. There is also a large body of animal and mechanism studies. No Phase 3 data was found |
| Kinds of study | Phase 2 trials with a placebo group. Studies that count nerve fibers in the cornea with a special microscope. Rodent and cell studies of cell protection and transplants |
| People studied | Adults with small fiber neuropathy linked to sarcoidosis. Adults with type 2 diabetes who reported nerve symptoms. No other groups of people |
| Checked by other labs | Several trials found the same cornea nerve and symptom results, but they share a core group of scientists [12], [18]. The receptor idea behind the peptide has added support from heart protection and islet transplant studies done with labs in Japan and Sweden. Members of the core group are co-authors on both, so these are not fully separate checks [5], [20] |
| Where the work comes from | Most of the human studies come from a fairly small group of scientists who share authors, and from research tied to Araim Pharmaceuticals |
| Longest study | Phase 2 trial periods lasting weeks. No human follow-up over several years was found |
| Approval | Experimental research compound. No approval from the FDA, the EMA or the MHRA for any use was found |
| Do the results agree | Yes within the sarcoidosis trials, which each reported better cornea nerve counts and fewer nerve symptoms. The receptor idea also holds up across animal studies of heart protection, nerve damage and islet transplants |
How it might work
In the early to middle 2000s, scientists reported that EPO’s tissue-protecting effects could be pulled apart from its red blood cell effects. The split showed up in the shape of the hormone and in the receptors it uses [1], [2]. ARA-290 was designed to use that split.
Two receptors
A receptor is the spot on a cell where a hormone attaches.
- The classic EPO receptor. This one drives red cell production. It is made of two identical EPOR units, a pair called a homodimer. It is found mainly on the young cells in bone marrow that grow into red blood cells.
- The innate repair receptor. A 2004 study reported that EPO seemed to protect tissue through a different, mixed receptor. It joins one EPOR unit with a unit called the beta-common receptor, also known as CD131 or CSF2RB [2]. Later papers named this mixed pair the innate repair receptor, or IRR [9].
ARA-290 is reported to favor the IRR. It barely grips the classic receptor at all. Scientists have proposed this as the structural reason it does not make red blood cells [3].
Why the shape matters
The 11 amino acids match a helix on the outer surface of folded EPO. That stretch is apart from the amino acids EPO needs to pair up the classic receptor and send the red cell signal [3].
A related animal study used a peptide built to copy the same 3D region. It protected tissue in heart protection models and showed no sign of a red blood cell effect. That backs the wider design logic for this peptide family [5].
Drugs that boost red cell production have a history of heart, vessel and blood clot safety concerns. This class of peptide is built to stay off the classic receptor, so scientists have proposed that it may avoid some of those concerns. The papers present this as reasoning from the mechanism. It is not a proven safety result in patients [4].
Found where tissue is hurt
IRR papers return often to one point. The receptor is reported to appear mainly on tissue that is injured, short of oxygen or under metabolic stress, and not on healthy tissue. That could explain how a peptide given to the whole body protects only certain tissue and does not broadly boost red cells [9].
A later drug review set this idea within the wider work on EPO-based peptides that do not make blood cells. It called the idea a “molecular switch” between the classic red cell pathway and the IRR pathway that protects tissue [16].
Signals after the receptor
Once the IRR is switched on, studies in several test systems have reported signals that keep cells from dying and that calm inflammation.
- In models of nerve pain, ARA-290 was linked to less activation of microglia in the spinal cord. Microglia are immune cells of the brain and spinal cord. Their activation is a sign of inflammation there, and it is thought to help keep long-term pain going [14].
- A review on neuropathy, meaning nerve damage, proposed IRR action as the reason to test ARA-290 in small fiber neuropathy. It summed up the cell-protecting and inflammation-calming signals reported after the receptor [17].
What the studies found
The papers on ARA-290 itself are few but growing. They cover early human trials in two kinds of nerve damage, studies that count nerve fibers, and a wider set of animal studies on cell protection.
Nerve damage in sarcoidosis
Sarcoidosis is an inflammatory disease that affects many body systems. Some patients also get small fiber neuropathy, or SFN. This is damage to small nerve fibers that lack the fatty coating called myelin. It is reported to cause a lot of pain and to lower quality of life [8]. One review called SFN in sarcoidosis an overlooked but medically important cause of long-term pain in these patients [10].
- An early review. One review paper looked at ARA-290 in patients with long-term nerve pain caused by sarcoidosis. It laid out the reasons for testing this EPO relative and the first trial results [11].
- A review of the trials. A related paper reviewed ARA-290 as an experimental treatment for SFN in sarcoidosis. It summed up the trial evidence building up in these patients [13].
- Symptoms and nerve fibers. In a trial with a placebo group, patients had lost small nerve fibers because of sarcoidosis. ARA-290 was linked to better reported nerve symptoms. It was also linked to a rise in nerve fiber density in the cornea, the clear front of the eye. That density is a countable, structural marker of small fiber health [12].
- A later trial. A follow-up trial used the name cibinetide and the same kind of patients. It reported more nerve fibers in the cornea, which backed up the earlier marker result. At one dose it also reported more regrowing nerve fibers in the skin [18].
- Animal pain models. In animals with nerve pain, ARA-290 was linked to long-lasting relief [7]. A related study found that the relief came together with a weaker microglia response in the spinal cord. That response is a proposed inflammation process behind long-term nerve pain [14].
Diabetes and nerve symptoms
One trial with a placebo group tested ARA-290 in adults with type 2 diabetes. These patients were a different group from the sarcoidosis trials, though some of the same scientists ran it. ARA-290 was linked to better measures of metabolic control and better reported nerve symptoms [15].
This result places ARA-290 within research on metabolism and diabetic nerve damage. Scientists remain interested in that area for this peptide, beyond the sarcoidosis trials.
Counting nerve fibers in the cornea
Corneal confocal microscopy is a way to see and count the small nerve fibers of the cornea without cutting into the eye. It shows up again and again as a measured outcome in the human studies of ARA-290. It adds a hard structural number to the symptom scores that patients report.
- One study looked at this measure directly. It reported that the size and density of cornea nerve fibers add value in diagnosing SFN and in judging how these patients respond to treatment [19].
- The first ARA-290 sarcoidosis trial [12] and the later cibinetide trial [18] each used cornea nerve fiber density as a primary or key secondary outcome.
Animal studies of cell protection
- Heart. An animal study tested a tissue-protecting peptide that does not make red blood cells and copies the 3D shape of EPO. In models of cardiac ischemia, meaning poor blood flow to the heart, it lowered signs of tissue injury. That supports the wider case for this peptide family [5].
- Transplants. In animal models of diabetes, cibinetide was linked to better function of islet allografts. These are insulin-making cell clusters transplanted from a donor. The authors proposed it as a use of IRR targeting for tissue injury tied to transplants [20].
- Roots of the field. All of this goes back to the first reports that EPO’s cell-protecting actions could be split in structure from its red cell actions [1], [2]. That work was later reviewed along with the patents on this class of compound [6].
Safety
In trials and in animals
- The Phase 2 trial in type 2 diabetes found no safety issues [15]. Two review papers on the sarcoidosis trials also described no safety issues [11], [13].
- The animal heart study [5] and the islet transplant study [20] reported no new safety problems and no cell-killing effect caused by the peptide.
- ARA-290 is built to stay off the classic red cell receptor. So scientists have proposed, from the mechanism, that it avoids the heart, vessel and blood clot risks long tied to drugs that boost red cells. This is still a proposed mechanism in the papers. It is not a confirmed safety finding in patients [4].
What is not known
- No Phase 3 trial data was found to confirm the results. The Phase 2 trials had fairly small numbers of people, which limits how sure anyone can be about the safety results.
- Long-term safety in people, beyond the weeks-long trial periods, has not been shown in the papers reviewed.
- No formal drug interaction study of ARA-290 was found.
- It is not fully settled how much of the safety picture comes from the IRR and how much from other possible signal routes [9], [16], [17].
Legal status in the US
- Not FDA approved. As of 2026, ARA-290 is an experimental compound. The FDA has not approved it for any use. The same is true of the EMA in Europe and the MHRA in the UK.
- Sport. The current World Anti-Doping Agency (WADA) Prohibited List does not name ARA-290. But class S2 of the list, which covers peptide hormones, growth factors, related substances and mimetics, bans innate repair receptor agonists at all times. That is the group ARA-290 is reported to belong to.
- Research use. It is supplied strictly for laboratory research, not for human use or use in competition.
Limits of the research
- No Phase 3 data. Every human result in this guide comes from Phase 2 work. No large trial to confirm those results was found.
- Small trials. The sarcoidosis and type 2 diabetes trials each enrolled fairly few people. That limits how far the results can be applied to wider groups.
- Indirect and self-reported measures. Cornea nerve fiber density is a structural marker. It does not directly measure how a patient does. The nerve symptom results lean heavily on scores that patients report themselves [12], [19].
- Sponsor and author overlap. Much of the human research comes from work tied to Araim Pharmaceuticals and from a fairly small group of scientists who share authors. Few outside groups have repeated it.
- Very different settings. SFN in sarcoidosis, nerve damage in type 2 diabetes, heart protection and islet transplants are separate fields. A result in one may not hold in another.
- Short studies only. The longest trial periods found lasted weeks. Safety and benefit past that point are not described in the papers reviewed.
- The mechanism is not complete. Studies with several partner labs support the IRR idea, though the same core scientists are co-authors on most of the ones cited here. The full chain of signals after the receptor, and how it relates to each reported effect, is still being worked out [9], [17].
- Missing negative results. As with any narrow field tied to a sponsor, bias in what gets published or reported cannot be ruled out.
ARA-290 has early human results in two kinds of nerve damage. They come from small, short trials, and no large trial has confirmed them.
References
Selected peer-reviewed references, each verified against the CrossRef API before inclusion. Ordered by date of publication.
- Leist M, Ghezzi P, Grasso G, Bianchi R, et al. (2004). Derivatives of Erythropoietin That Are Tissue Protective But Not Erythropoietic. Science, 305(5681), 239–242. DOI: 10.1126/science.1098313
- Brines M, Grasso G, Fiordaliso F, Sfacteria A, et al. (2004). Erythropoietin mediates tissue protection through an erythropoietin and common β-subunit heteroreceptor. Proceedings of the National Academy of Sciences, 101(41), 14907–14912. DOI: 10.1073/pnas.0406491101
- Brines M, Patel N, Villa P, Brines C, et al. (2008). Nonerythropoietic, tissue-protective peptides derived from the tertiary structure of erythropoietin. Proceedings of the National Academy of Sciences, 105(31), 10925–10930. DOI: 10.1073/pnas.0805594105
- Brines M, Cerami A (2008). Erythropoietin-mediated tissue protection: reducing collateral damage from the primary injury response. Journal of Internal Medicine, 264(5), 405–432. DOI: 10.1111/j.1365-2796.2008.02024.x
- Ueba H, Brines M, Yamin M, Umemoto T, et al. (2010). Cardioprotection by a nonerythropoietic, tissue-protective peptide mimicking the 3D structure of erythropoietin. Proceedings of the National Academy of Sciences, 107(32), 14357–14362. DOI: 10.1073/pnas.1003019107
- Dumont F, Bischoff P (2010). Non-erythropoietic tissue-protective peptides derived from erythropoietin: WO2009094172. Expert Opinion on Therapeutic Patents, 20(5), 715–723. DOI: 10.1517/13543771003627464
- Swartjes M, Morariu A, Niesters M, Brines M, et al. (2011). ARA290, a Peptide Derived from the Tertiary Structure of Erythropoietin, Produces Long-term Relief of Neuropathic Pain. Anesthesiology, 115(5), 1084–1092. DOI: 10.1097/aln.0b013e31822fcefd
- Judson M (2011). Small fiber neuropathy in sarcoidosis: Something beneath the surface. Respiratory Medicine, 105(1), 1–2. DOI: 10.1016/j.rmed.2010.10.005
- Brines M, Cerami A (2012). The Receptor That Tames the Innate Immune Response. Molecular Medicine, 18(3), 486–496. DOI: 10.2119/molmed.2011.00414
- Heij L, Dahan A, Hoitsma E (2012). Sarcoidosis and Pain Caused by Small-Fiber Neuropathy. Pain Research and Treatment, 2012, 1–6. DOI: 10.1155/2012/256024
- Niesters M, Swartjes M, Heij L, Brines M, et al. (2013). The erythropoietin analog ARA 290 for treatment of sarcoidosis-induced chronic neuropathic pain. Expert Opinion on Orphan Drugs, 1(1), 77–87. DOI: 10.1517/21678707.2013.719289
- Dahan A, Dunne A, Swartjes M, Proto P, et al. (2013). ARA 290 Improves Symptoms in Patients with Sarcoidosis-Associated Small Nerve Fiber Loss and Increases Corneal Nerve Fiber Density. Molecular Medicine, 19(1), 334–345. DOI: 10.2119/molmed.2013.00122
- van Velzen M, Heij L, Niesters M, Cerami A, et al. (2014). ARA 290 for treatment of small fiber neuropathy in sarcoidosis. Expert Opinion on Investigational Drugs, 23(4), 541–550. DOI: 10.1517/13543784.2014.892072
- Swartjes M, van Velzen M, Niesters M, Aarts L, et al. (2014). ARA 290, a Peptide Derived from the Tertiary Structure of Erythropoietin, Produces Long-Term Relief of Neuropathic Pain Coupled with Suppression of the Spinal Microglia Response. Molecular Pain, 10, 13. DOI: 10.1186/1744-8069-10-13
- Brines M, Dunne A, van Velzen M, Proto P, et al. (2014). ARA 290, a Nonerythropoietic Peptide Engineered from Erythropoietin, Improves Metabolic Control and Neuropathic Symptoms in Patients with Type 2 Diabetes. Molecular Medicine, 20(1), 658–666. DOI: 10.2119/molmed.2014.00215
- Collino M, Thiemermann C, Cerami A, Brines M (2015). Flipping the molecular switch for innate protection and repair of tissues: Long-lasting effects of a non-erythropoietic small peptide engineered from erythropoietin. Pharmacology & Therapeutics, 151, 32–40. DOI: 10.1016/j.pharmthera.2015.02.005
- Dahan A, Brines M, Niesters M, Cerami A, et al. (2016). Targeting the innate repair receptor to treat neuropathy. PAIN Reports, 1(1), e566. DOI: 10.1097/pr9.0000000000000566
- Culver D, Dahan A, Bajorunas D, Jeziorska M, et al. (2017). Cibinetide Improves Corneal Nerve Fiber Abundance in Patients With Sarcoidosis-Associated Small Nerve Fiber Loss and Neuropathic Pain. Investigative Ophthalmology & Visual Science, 58(6), BIO52. DOI: 10.1167/iovs.16-21291
- Brines M, Culver D, Ferdousi M, Tannemaat M, et al. (2018). Corneal nerve fiber size adds utility to the diagnosis and assessment of therapeutic response in patients with small fiber neuropathy. Scientific Reports, 8(1), 4734. DOI: 10.1038/s41598-018-23107-w
- Yao M, Watanabe M, Sun S, Tokodai K, et al. (2020). Improvement of Islet Allograft Function Using Cibinetide, an Innate Repair Receptor Ligand. Transplantation, 104(10), 2048–2058. DOI: 10.1097/tp.0000000000003284
Related compounds
- SS-31: Four-amino-acid peptide (elamipretide) that targets mitochondria, tested in animals and people.
- Semax: Lab-made peptide built from a piece of the hormone ACTH, approved in Russia for stroke.
- Thymosin Alpha-1: Immune peptide from the thymus, sold as an approved drug in many countries.