Ipamorelin is a lab-made chain of five amino acids that makes the pituitary gland release growth hormone. In animals it did this without raising cortisol, prolactin or ACTH. Human data come from one single-dose study and one phase 2 trial that missed its main goal.
In brief
- It raises pulses of growth hormone without pushing up ACTH or cortisol, unlike the older compounds GHRP-6 and GHRP-2.
- Its effects on bone and lean mass have been measured in rats and mice, including bone loss caused by steroid drugs called glucocorticoids.
- It leaves the blood fast, with a half-life of about 2 hours in a single-dose study of human volunteers.
What ipamorelin is
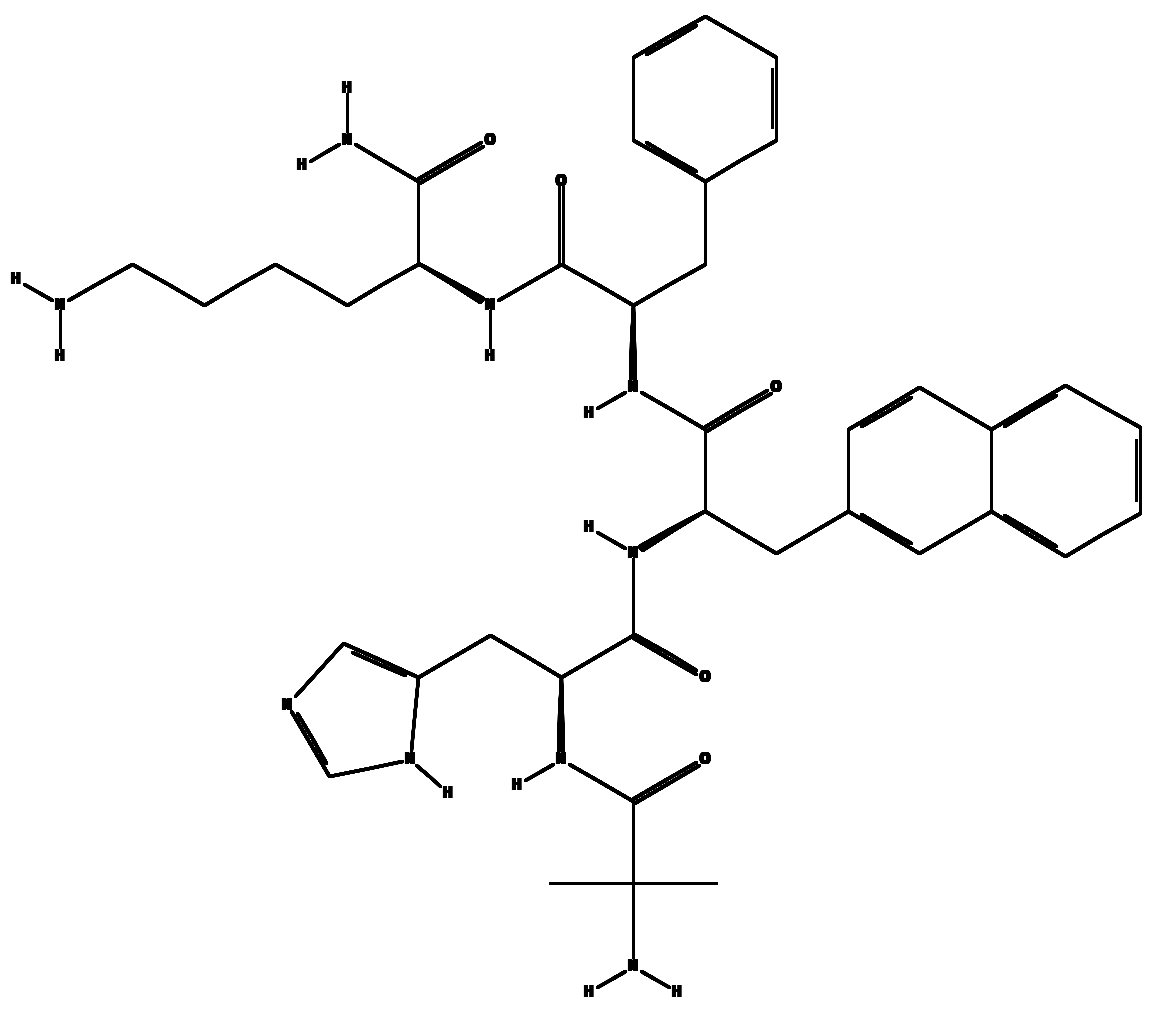
Ipamorelin is a lab-made peptide that makes the body release growth hormone (GH). Most of what is known about it comes from rats, mice, pigs and cells in a dish. The human record is thin. It has one single-dose study in healthy volunteers [3], one trial in bowel surgery patients [12], and a few scattered drug reports. That trial was a phase 2 study run at many hospitals. It finished in 2014 and missed its main goal [12]. As of 2026, the FDA, the EMA and the MHRA have not approved ipamorelin for any use. In most places it is still a research-only chemical.
A peptide is a short chain of amino acids, the building blocks of protein. Ipamorelin has five of them (Aib-His-D-2-Nal-D-Phe-Lys-NH2) and weighs about 712 Da.
It is one of the growth hormone secretagogues, or GHS. These compounds prompt the pituitary gland, a gland at the base of the brain, to let out GH. They do it by switching on a receptor called GHSR-1a. A receptor is a spot on a cell where a signal attaches. GHSR-1a is the same one used by ghrelin, a peptide the body makes itself [1].
Scientists at Novo Nordisk first described ipamorelin in 1998. They called it “the first selective growth hormone secretagogue” [1]. What sets it apart is which hormones it leaves alone. Older compounds of this type are called GHRPs, short for growth hormone-releasing peptides. Two of them, GHRP-6 and GHRP-2, also pushed up two other hormones in pigs. Those are ACTH and cortisol. Cortisol is a stress hormone, and ACTH is the pituitary signal that calls for it. In animal tests, ipamorelin gave a strong GH response at doses that did not raise either one in the blood. It did not change prolactin, a milk hormone, either [1].
The first plan was to turn it into a medicine for conditions where GH and IGF-1 signals run low. Two examples were catabolic states, where the body breaks down its own tissue, and postoperative ileus, where the gut is slow to restart after surgery. The ileus work was dropped after the 2014 trial [12].
How much research there is
Plenty of animal and lab work, two published human studies, and one failed trial.
| Question | Answer |
|---|---|
| Published studies | More than 30. This guide cites 27 key ones. |
| What was tested | Mostly live rats and mice, receptor and pituitary samples in a dish, and lab chemistry methods |
| People studied | One published phase 1 study of blood levels and GH response [3], and one published phase 2 trial in bowel surgery [12] |
| How it works | It switches on GHSR-1a, the ghrelin receptor. Animal studies saw very little effect on ACTH, cortisol or prolactin |
| Drug development | The ileus project was stopped after the 2014 proof-of-concept trial missed its main goal |
| Approval | None from the FDA, EMA or MHRA for any use |
| Checked by other labs | Outside groups backed the core selectivity result in studies of drug structure and receptor behavior |
| How the body handles it | Measured in rats and dogs. In people there is a limited single-dose profile only, with nothing published on repeat doses |
The human data set is much smaller than the animal one. The only finished trial of whether it works came back negative on its main measure. Both points matter when weighing any claim about the compound.
How it might work
Ipamorelin is classed as a selective agonist of GHSR-1a. An agonist is a compound that switches a receptor on. GHSR-1a is a G-protein coupled receptor, a common type of cell switch. It sits mainly in the pituitary gland and in the hypothalamus, a part of the brain [1], [15].
GH is made by pituitary cells called somatotrophs, which store it in small packets. When ipamorelin attaches to the receptor, calcium moves inside these cells and the packets empty. Papers most often point to how selective it is next to the older peptide GHRPs. That is the reason scientists study it.
Growth hormone without the stress hormones
Raun and colleagues wrote the discovery paper. They ran ipamorelin against GHRP-6 in rats, and against GHRP-6 and GHRP-2 in pigs [1].
- Ipamorelin was about as strong as GHRP-6 at releasing GH.
- In pigs, even the doses that gave the most GH caused no significant rise in blood ACTH or cortisol. Both of the other compounds did raise those two. None of the three changed prolactin.
The authors decided ipamorelin was its own subtype inside the GHS class. It kept its power to release GH. It had cut loose from the pituitary pathways that control stress hormones and milk hormones.
Later teams tried to get the same selectivity in versions that could be taken by mouth [13], [14], [16]. The pattern held across several peptidomimetics, which are compounds built to act like peptides. That hints that the parts of the molecule behind GH release can be split from the parts behind cortisol or prolactin release.
Other work on the structure of GHSR-1a agonists backs the first report [1], but only indirectly. Ankersen and colleagues built a series of peptides on the ipamorelin frame. Changing the structure kept, or even widened, the gap between GH release and ACTH or cortisol release [13], [14]. Later binding studies of peptidomimetic GHS compounds mapped which features explain selectivity for GHSR-1a over other G-protein coupled receptors [18], [19].
One point needs stress. The claim that ipamorelin spares cortisol and prolactin rests mostly on animal data. No peer-reviewed paper has formally tracked ACTH, cortisol and prolactin in people given repeated doses.
Side by side with other compounds
The discovery paper compared four compounds: ipamorelin, GHRP-6, GHRP-2 and GHRH (growth hormone-releasing hormone). In rats, ipamorelin raised GH about as much as GHRP-6 did. In pigs, ACTH and cortisol after ipamorelin were no different from the levels seen after GHRH. GHRP-6 and GHRP-2 raised both [1].
Malmlöf and colleagues later tested a new oral secretagogue made from ipamorelin. They gave rats methylprednisolone first. It is a glucocorticoid, a kind of steroid drug. GH release held up anyway [17].
Because of results like these, ipamorelin is treated as a tool compound. Scientists use it to look at GH effects alone, without the ACTH and cortisol system muddying the picture. There is a catch. How much cortisol and prolactin a GHRP releases can change with the species, the dose and the way it is given. So the clean result from the first pig studies may not hold for every way of dosing people.
Pulses of growth hormone
The body does not release GH in a steady stream. It comes in bursts, with the biggest ones during deep sleep and between meals. Ghrelin and lab-made copies of it, ipamorelin among them, make each burst taller. They do not cause a constant raised level [1], [3].
The phase 1 study gave healthy men single doses into a vein [3].
- Peak GH rose as the dose rose.
- GH fell back toward its starting level within about 2 to 3 hours.
- The half-life of ipamorelin in plasma was put at about 2 hours. Half-life is the time it takes for half of a compound to leave the blood.
Why would pulses matter? Constant GH exposure with no pulses, such as a drip of recombinant (lab-made) GH, has been linked to different effects in the body than natural bursts. But for ipamorelin, no controlled human trial has shown that pulses from a secretagogue act differently from injected recombinant GH.
IGF-1 further down the chain
Once the pituitary lets GH out, it acts mostly on the liver and on outlying tissues. There it triggers the making of IGF-1, or insulin-like growth factor 1. IGF-1 carries out many of the tissue-building effects tied to GH.
- Rats given ipamorelin over a long period grew longer bones, more so at higher doses. The growth tracked with higher IGF-1 in the blood [2].
- A later study gave ipamorelin together with glucocorticoids. These drugs lower blood IGF-1 and markers of bone formation. Ipamorelin partly reversed both drops [5].
- Another team took somatotrophs from young female rats after long ipamorelin exposure and studied the loose cells in a dish. The way the cells stored and released GH had changed. So a secretagogue may also alter, over time, how much the GH-making cells can do [4].
What the studies found
Most of these studies used animals or cells. Human studies are marked as such.
How fast GH is released
In animals. Raun and colleagues set out the basic drug profile [1]. Rats got single doses into a vein. More ipamorelin meant more GH. The top response matched GHRP-6 and beat GHRH given in equal molar amounts. Pigs showed strong GH release too, with none of the ACTH and cortisol rises that GHRP-6 and GHRP-2 caused.
In people. Gobburu and colleagues ran the phase 1 study in healthy male volunteers. Doses went into a vein and ranged from 0.005 to 0.08 mg/kg [3]. GH peaked between 0.25 and 0.75 hours after the dose. Total GH exposure over time, called the area under the curve, went up in step with dose. The team fitted a math model linking ipamorelin in plasma to the GH response. It was the first time anyone had put numbers on the compound’s behavior in humans.
Other routes. Animal studies also tried a nasal spray and other ways of giving it [20]. The share absorbed through the nose was modest but could be measured. Blood levels high enough to release GH could be reached that way in animals.
Bone
- Bone length. Young rats dosed for several weeks had longer shin bones (tibias) and more IGF-1 in the blood. Both effects grew with dose. This points to a building effect on the growth plate [2].
- Bone mineral. Svensson and colleagues gave adult female rats repeated doses of ipamorelin or GHRP-6. Both raised bone mineral content. They credited steady stimulation of the GH/IGF-1 axis [6].
- Bone loss from steroids. In rats on a glucocorticoid during the same period, ipamorelin partly offset the fall in markers of bone formation. In this rodent model, that hints at protection against the bone breakdown these drugs cause [5].
These results are the animal case for studying ipamorelin in two groups: people in catabolic states and people taking glucocorticoids. No controlled human trial has reported bone outcomes.
Fat, protein and body weight
- Fat. Lall and colleagues looked at how GHS compounds change body fat and body makeup in rodents apart from GH [7]. Switching on GHSR changed fat mass in ways GH release alone could not fully explain. That suggests direct effects through GHSR-1a found outside the pituitary.
- Nitrogen balance. Aagaard and colleagues gave ipamorelin and GH to rats treated with glucocorticoids. The changes in urea production and nitrogen kept in the body fit an anti-catabolic effect, meaning less tissue breakdown [8]. These are blood and urine markers of protein use in animals. Controlled human studies have not repeated them.
- Weight loss from chemotherapy. A 2024 study used ferrets that were losing weight on the cancer drug cisplatin. It tested ipamorelin and a related GHSR-1a agonist, anamorelin. Both eased the weight loss linked to cachexia, a wasting condition. Only anamorelin also worked against vomiting, through an action in the brain [21].
The gut after surgery, and the human trial
Helsinn Therapeutics developed ipamorelin for postoperative ileus, working with the original Novo Nordisk compound.
The case for a trial came from rats. Venkova and colleagues [9] and Greenwood-Van Meerveld and colleagues [10] opened the abdomen in surgery. Afterward, food moved through the gut again sooner in rats that got ipamorelin. A later rodent study found that GHSR agonists, ipamorelin included, dulled pain signals from both the organs and the body wall [11].
Beck and colleagues reported the key human trial in 2014 [12].
- Design: prospective, randomized, controlled, proof-of-concept.
- Who: 114 patients having planned bowel resection, surgery that removes part of the bowel.
- Treatment: ipamorelin or placebo into a vein for up to seven days after surgery.
- Main measure: time until the gut worked again.
- Result: patients mostly tolerated ipamorelin well. It was not better than placebo on the main measure by a statistically significant margin. The ileus project was then shut down.
No other large randomized trial of ipamorelin has appeared in a peer-reviewed journal. The compound does show up in a number of anti-doping lab papers. There it is one of the substances that tests look for when checking athletes for GHS misuse [22], [23], [24].
How it compares within its class
Studies that link structure to activity give a fairly detailed view of this drug class.
| Compared with | What was found |
|---|---|
| GHRP-6 and GHRP-2 | Ipamorelin equaled GHRP-6 at releasing GH. It skipped the ACTH and cortisol response that came with GHRP-6 and GHRP-2 [1] |
| NN703 | Novo Nordisk designed this oral secretagogue as the successor to injected ipamorelin. Selectivity was similar and more of it was absorbed by mouth [14], [16] |
| Anamorelin | The GHSR-1a agonist furthest along in human testing. It releases GH in the same basic way and adds an anti-vomiting effect through brain pathways [21] |
| PET imaging tracers | Peptidomimetic versions of ipamorelin have been made into radioactive tracers for scanning the ghrelin receptor. This work confirmed which structural core is needed to engage GHSR-1a [25] |
Reviews on low testosterone (hypogonadism) and body makeup place ipamorelin with the other GHSR-1a agonists. They treat these as research tools, not as agents proven in the clinic [26].
Safety
In animals
- Rats, mice and pigs mostly tolerated the doses used in drug studies [1], [2].
- Doses that released GH did not raise ACTH or corticosterone in rats and pigs [1].
- Published drug studies report no signs of sudden toxicity in rodents, at doses into a vein of up to several mg/kg.
- No formal lifetime cancer study or reproductive toxicity study has been published in a peer-reviewed journal.
In people
There is not much published.
- Healthy men in the phase 1 study took single doses into a vein of up to 0.08 mg/kg. None had a serious adverse event [3].
- In the phase 2 bowel surgery trial of 114 patients, ipamorelin was reported as mostly well tolerated. Its side effects were broadly similar to placebo [12].
- GHSR-1a agonists as a class have been reported to raise blood sugar and insulin. The cause is the metabolic action of the GH they release. Detailed data on how people handle sugar on ipamorelin itself have not been published.
What is not known
- There is no published long-term human safety data from repeated dosing.
- There are no formal studies in people of how it interacts with other drugs.
- Nothing is published on use in pregnancy, in breastfeeding or in children.
- Nobody has studied in an organized way how it interacts in people with GHRH, with the body’s own ghrelin signals, or with appetite control.
- Switching on GHSR-1a makes the body’s own GH pulses larger. Its effects in people who have, or may have, a cancer that responds to GH have not been tested.
- Lab analyses have found ipamorelin in black-market growth products. They show that the purity and identity of unverified research-grade material cannot be taken for granted [27].
Legal status in the US
- Not FDA approved. Ipamorelin has no approval from the FDA for any use. The same is true of the EMA in Europe and the MHRA in the UK.
- Banned in sport. The World Anti-Doping Agency lists it as a growth hormone secretagogue under S2 (Peptide Hormones, Growth Factors, Related Substances and Mimetics). It is banned at all times, in and out of competition.
- Research use. It is sold as a research-only chemical, not for human use.
Limits of the research
- Mostly animal and lab data. Little human research has been published. The strongest signal in animals is the boost to pulsed GH release, and how that works is well understood. Nobody has shown that it leads to outcomes that matter for patients.
- The key trial was negative. The 2014 phase 2 ileus study missed its main goal [12]. The project ended. No follow-up trial of that kind has been registered or published since.
- The hormone-sparing claim comes from animals. The selectivity was worked out mainly in rats and pigs [1]. No one has published an organized hormone profile in people over repeated doses.
- No repeat-dose data on how the body handles it. The 1999 Gobburu study described single doses only [3]. Steady-state levels, build-up in the body and fading of the receptor response with repeated doses have not been formally measured in humans.
- Early work came from one company. Most of the discovery and early drug papers came out of Novo Nordisk projects. Outside support for the core selectivity result comes largely from structure and lab-analysis studies, not from independent trials of whether it works.
- Recent papers are mostly about detection. A large share of the newer literature covers anti-doping test methods [22], [23], [24], not new drug science. That reflects a compound moving through unregulated supply chains, not one in active medical development.
Ipamorelin releases growth hormone in animals and in healthy volunteers. Its one trial in patients missed its main goal.
References
Selected peer-reviewed references. Ordered by topic then date of publication.
- Raun K, Hansen BS, Johansen NL, et al. (1998). Ipamorelin, the first selective growth hormone secretagogue. European Journal of Endocrinology, 139(5), 552–561. DOI. PMID: 9849822
- Johansen PB, Nowak J, Skjaerbaek C, et al. (1999). Ipamorelin, a new growth-hormone-releasing peptide, induces longitudinal bone growth in rats. Growth Hormone & IGF Research, 9(2), 106–113. DOI. PMID: 10373343
- Gobburu JV, Agersø H, Jusko WJ, et al. (1999). Pharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers. Pharmaceutical Research, 16(9), 1412–1416. DOI. PMID: 10496658
- Jiménez-Reina L, Cañete R, de la Torre MJ, et al. (2002). Influence of chronic treatment with the growth hormone secretagogue ipamorelin, in young female rats: somatotroph response in vitro. Histology and Histopathology, 17(3), 707–714. DOI. PMID: 12168778
- Andersen NB, Malmlöf K, Johansen PB, et al. (2001). The growth hormone secretagogue ipamorelin counteracts glucocorticoid-induced decrease in bone formation of adult rats. Growth Hormone & IGF Research, 11(5), 266–272. DOI. PMID: 11735244
- Svensson J, Lall S, Dickson SL, et al. (2000). The GH secretagogues ipamorelin and GH-releasing peptide-6 increase bone mineral content in adult female rats. Journal of Endocrinology, 165(3), 569–577. DOI. PMID: 10828840
- Lall S, Tung LY, Ohlsson C, et al. (2001). Growth hormone (GH)-independent stimulation of adiposity by GH secretagogues. Biochemical and Biophysical Research Communications, 280(1), 132–138. DOI. PMID: 11162489
- Aagaard NK, Grøfte T, Greisen J, et al. (2009). Growth hormone and growth hormone secretagogue effects on nitrogen balance and urea synthesis in steroid treated rats. Growth Hormone & IGF Research, 19(5), 426–431. DOI. PMID: 19231263
- Venkova K, Mann W, Nelson R, et al. (2009). Efficacy of ipamorelin, a novel ghrelin mimetic, in a rodent model of postoperative ileus. Journal of Pharmacology and Experimental Therapeutics, 329(3), 1110–1116. DOI. PMID: 19289567
- Greenwood-Van Meerveld B, Tyler K, Mohammadi E, et al. (2012). Efficacy of ipamorelin, a ghrelin mimetic, on gastric dysmotility in a rodent model of postoperative ileus. Journal of Experimental Pharmacology, 4, 149–155. DOI. PMID: 27186127
- Mohammadi EN, Louwies T, Pietra C, et al. (2020). Attenuation of visceral and somatic nociception by ghrelin mimetics. Journal of Experimental Pharmacology, 12, 267–274. DOI. PMID: 32801950
- Beck DE, Sweeney WB, McCarter MD, et al. (2014). Prospective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients. International Journal of Colorectal Disease, 29(12), 1527–1534. DOI. PMID: 25331030
- Ankersen M, Johansen NL, Madsen K, et al. (1998). A new series of highly potent growth hormone-releasing peptides derived from ipamorelin. Journal of Medicinal Chemistry, 41(19), 3699–3704. DOI. PMID: 9733495
- Hansen TK, Ankersen M, Hansen BS, et al. (1998). Novel orally active growth hormone secretagogues. Journal of Medicinal Chemistry, 41(19), 3705–3714. DOI. PMID: 9733496
- Ahnfelt-Rønne I, Nowak J, Olsen UB, et al. (2001). Do growth hormone-releasing peptides act as ghrelin secretagogues? Endocrine, 14(1), 133–135. DOI. PMID: 11322495
- Hansen BS, Raun K, Nielsen KK, et al. (1999). Pharmacological characterisation of a new oral GH secretagogue, NN703. European Journal of Endocrinology, 141(2), 180–189. DOI. PMID: 10427162
- Malmlöf K, Johansen PB, Haahr PM, et al. (1999). Methylprednisolone does not inhibit the release of growth hormone after intravenous injection of a novel growth hormone secretagogue in rats. Growth Hormone & IGF Research, 9(6), 445–450. DOI. PMID: 10629165
- Hansen TK, Ankersen M, Raun K, et al. (2001). Highly potent growth hormone secretagogues: hybrids of NN703 and ipamorelin. Bioorganic & Medicinal Chemistry Letters, 11(14), 1915–1918. DOI. PMID: 11459660
- Ferro P, Krotov G, Zvereva I, et al. (2017). Structure-activity relationship for peptidic growth hormone secretagogues. Drug Testing and Analysis, 9(1), 87–95. DOI. PMID: 26811125
- Johansen PB, Hansen KT, Andersen JV, et al. (1998). Pharmacokinetic evaluation of ipamorelin and other peptidyl growth hormone secretagogues with emphasis on nasal absorption. Xenobiotica, 28(11), 1083–1092. DOI. PMID: 9879640
- Lu Z, Ngan MP, Liu JYH, et al. (2024). The growth hormone secretagogue receptor 1a agonists, anamorelin and ipamorelin, inhibit cisplatin-induced weight loss in ferrets. Physiology & Behavior, 284, 114644. DOI. PMID: 39043357
- Semenistaya E, Zvereva I, Thomas A, et al. (2015). Determination of growth hormone releasing peptides metabolites in human urine after nasal administration of GHRP-1, GHRP-2, GHRP-6, hexarelin, and ipamorelin. Drug Testing and Analysis, 7(10), 919–925. DOI. PMID: 25869809
- Thomas A, Delahaut P, Krug O, et al. (2012). Metabolism of growth hormone releasing peptides. Analytical Chemistry, 84(23), 10252–10259. DOI. PMID: 23101768
- Timms M, Hall N, Levina V, et al. (2014). A high-throughput LC-MS/MS screen for GHRP in equine and human urine, featuring peptide derivatization for improved chromatography. Drug Testing and Analysis, 6(10), 985–995. DOI. PMID: 24574167
- Fowkes MM, Lalonde T, Yu L, et al. (2018). Peptidomimetic growth hormone secretagogue derivatives for positron emission tomography imaging of the ghrelin receptor. European Journal of Medicinal Chemistry, 157, 1500–1511. DOI. PMID: 30282322
- Sinha DK, Balasubramanian A, Tatem AJ, et al. (2020). Beyond the androgen receptor: the role of growth hormone secretagogues in the modern management of body composition in hypogonadal males. Translational Andrology and Urology, 9(Suppl 2), S149–S159. DOI. PMID: 32257855
- Krug O, Thomas A, Malerød-Fjeld H, et al. (2018). Analysis of new growth promoting black market products. Growth Hormone & IGF Research, 41, 1–6. DOI. PMID: 29864719
Related compounds
- CJC-1295 No DAC: Short-acting lab-made copy of GHRH, tested mostly in animals for pulses of growth hormone.
- Ipamorelin + CJC-1295: Two lab-made peptides that release growth hormone by different routes, studied as a pair.
- Tesamorelin: Lab-made copy of a growth hormone signal, FDA approved to cut deep belly fat in HIV lipodystrophy.