Tesamorelin is a lab-made copy of the natural signal that tells the body to release growth hormone. The FDA approved it in 2010 for one use: cutting deep belly fat in people with HIV-related lipodystrophy. Studies on liver fat and thinking skills are much smaller.
In brief
- The FDA approved it for one use, HIV-related lipodystrophy, and its large human safety record covers more than 800 Phase 3 subjects plus groups followed for years.
- Beyond that use, scientists test it for deep belly fat, fatty liver (NAFLD) markers, liver scarring, and age-related decline in thinking skills in adults with HIV.
- It switches on the GHRH receptor in the pituitary, so the body releases its own growth hormone in pulses and the brain's feedback control stays in place.
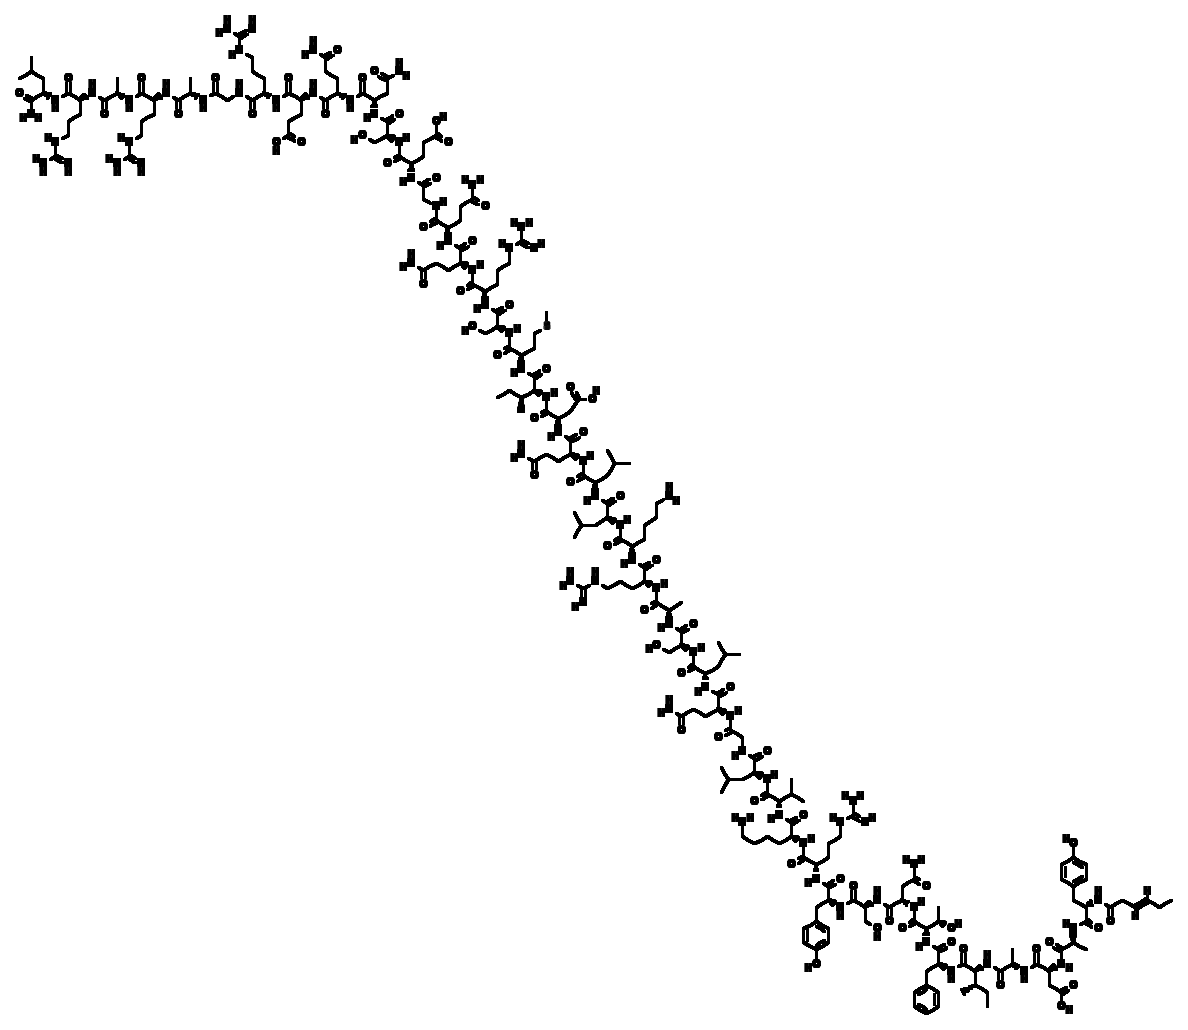
What tesamorelin is
Tesamorelin is a lab-made peptide that has been tested in people, not only in animals. Its Phase 3 trials enrolled over 800 subjects, and some groups were followed for years [5,6]. Few peptides of its kind have this much human data.
The FDA approved it in November 2010 for one use. It lowers visceral adipose tissue (VAT), the deep fat around the organs in the belly, when there is too much of it. The approval covers only people with HIV who have lipodystrophy, a change in where the body stores fat [3]. That is still the only approved use.
Scientists have also tested it for liver fat, thinking skills, aging and body composition in people without HIV. Those studies are far fewer and smaller.
A peptide is a short chain of amino acids, the building blocks of protein. This one has 44. It copies human growth hormone-releasing hormone, written GHRH(1-44). GHRH is the signal that tells the pituitary gland to release growth hormone (GH).
One thing sets it apart from natural GHRH. A small cap called trans-3-hexenoyl (tHex) is attached to the front end of the chain, the N-terminus. The cap keeps an enzyme called dipeptidyl peptidase-4 (DPP-4) from cutting the chain. The peptide then lasts long enough in the blood for one injection under the skin per day. It still fully switches on the GHRH receptor on somatotrophs, the pituitary cells that make GH [1,2].
Theratechnologies developed it. Its research name was TH9507. It was sold as Egrifta, and later as a reformulated product called Egrifta SV. Health Canada approved it in 2014. The MHRA in the UK and the EMA in Europe have not. The World Anti-Doping Agency (WADA) puts it on its Prohibited List in class S2 (Peptide Hormones, Growth Factors, Related Substances and Mimetics) [4].
This guide sums up the research for people who study the compound. Nothing in it is medical advice, and patients are not its intended readers.
How much research there is
The strongest evidence is for HIV-related lipodystrophy. Every other use rests on smaller studies, most of them early-stage.
| Topic | Kind of evidence | Main studies | Who was studied | What it showed |
|---|---|---|---|---|
| Deep belly fat (VAT) in HIV lipodystrophy | Phase 3 randomized trials. This is the approved use | Falutz 2007 [5]; Falutz 2010 pooled [6] | 806 people randomized in Phase 3 | VAT fell 15 to 18% from the starting level. It came back after stopping |
| Long-term safety in HIV lipodystrophy | Phase 3 extension phases | Falutz 2008 AIDS [11]; Phase 3 extensions [6] | 246 people stayed on the drug through week 52 | Reactions where the shot went in, a small rise in glucose, and a need to check IGF-1 |
| Liver fat and fatty liver (NAFLD) in HIV | Randomized trials. The 2019 trial used biopsy | Stanley 2014 [16]; Stanley 2019 [17] | 50 plus 61 people randomized | In the 2019 trial, liver fat dropped about 37% in relative terms. Scarring advanced in fewer people |
| Signs of inflammation | Substudy of Phase 3 | Stanley 2011 [23] | 410 people from the first Phase 3 trial | Changes in tPA, PAI-1 and adiponectin tracked with VAT loss |
| Predicted heart risk | Subanalysis done after the trials | Grinspoon 2025 [24]; McLaughlin 2023 [25] | Pooled Phase 3 | ASCVD scores got better. No data on real heart events (MACE) |
| Thinking skills in HIV | Phase 2 randomized open-label trial, negative | Ellis 2025 [19] | 73 people randomized | No statistically significant benefit |
| Body composition and muscle | One small randomized trial and one secondary analysis of Phase 3 scans | Makimura 2014 [20]; Adrian 2019 [22] | 39 obese adults; 341 people from Phase 3 | Less fat inside muscle. A sign of better energy use in muscle |
| Blood sugar in diabetes without HIV | Phase 2 randomized trial | Clemmons 2017 [15] | 53 people with type 2 diabetes | HbA1c did not get worse over 12 weeks |
| How the body handles it | Animal studies and a population PK/PD model | Ferdinandi 2007 [1]; González-Sales 2015 [9] | Animals; 41 healthy people and people with HIV | Half-life of about 26 to 38 minutes [26]. GH and IGF-1 response mapped |
How it works
It switches on the GHRH receptor
- The target. Its target is the growth hormone-releasing hormone receptor (GHRHR). This is a class B G-protein-coupled receptor. Somatotrophs carry a lot of it.
- The chain of signals. Like natural GHRH(1-44), it grips the receptor’s N-terminal domain outside the cell and the region next to the cell membrane. A protein called Gsα then turns on adenylate cyclase. A messenger called cAMP builds up. Protein kinase A then turns on the GH1 gene, which makes GH [1,7].
- The cap stays out of the way. The tHex group sits on the N-terminus. It does not cover Tyr1, Ala2 and Asp3, the three amino acids that grip the receptor. So its strength at GHRHR is about the same as natural GHRH [1].
It works one step above the pituitary. It prompts the body’s own system and does not replace GH. The hypothalamus and a hormone called somatostatin still hold GH release in check through negative feedback. GH still comes out in pulses, and the wider GH system keeps its normal shape [7,8]. Lab-made human growth hormone (rhGH) is different. It skips pituitary control altogether.
Why it lasts longer than natural GHRH
- Natural GHRH(1-44) has a half-life in the blood of roughly 6 to 7 minutes. The main reason is that DPP-4 cuts it between Ala2 and Asp3 [1].
- The tHex group physically blocks DPP-4 from reaching that bond. Half-life rose to about 26 to 38 minutes. That figure comes from healthy subjects and HIV-infected patients after 14 days of doses under the skin [26].
- In 2015, González-Sales and colleagues built a population PK/PD model from Phase 1 data on 41 people. They got 1 or 2 mg a day for 14 days. The model treated each dose as setting off GH release for a limited time. It predicted GH and IGF-1 levels well [9].
- Ferdinandi and colleagues tested TH9507 before human trials, in 2007. They found it was selective for its receptor and did not act on related class B GPCRs. Its toxicology results were favorable in rodents and in non-rodent species [1].
GH comes in pulses
In clinical studies, the usual dose was 2 mg under the skin once a day before bed. It made the body’s own nighttime GH pulses bigger. It did not create a constant GH level above the normal range [5,6].
Scientists tracked GH over 24 hours in people from the Phase 3 trials. Peak GH and average GH went up. The number of pulses and the low points between them stayed the same [6,14].
The pulse pattern is thought to matter for how well the signal carries downstream. Constant GH exposure is linked to tachyphylaxis, a fading response, and to metabolic side effects. Pulsed release appears to avoid both [8,14].
IGF-1 rises
Once the pituitary releases GH, it acts on GH receptors in the liver. That turns on the IGF1 gene. IGF-1 in the blood then rises in step with GH exposure.
- In the pooled Phase 3 data, IGF-1 was about 80 to 180% above baseline at week 26. A minority of patients went over the upper limit of normal for their age [5,6].
- IGF-1 carries many of the effects credited to the drug. These include fat breakdown in fat cells, fat burning in the liver, and protein building in skeletal muscle.
- The IGF-1 rise is the main marker of the drug’s action. So most clinical protocols call for IGF-1 checks from time to time. Dosing is paused if levels stay over the reference range [3,6,26].
Why deep belly fat shrinks
The best-known effect is a drop in VAT that spares other fat. Three linked steps are thought to explain it:
- GH directly turns on hormone-sensitive lipase, a fat-releasing enzyme, in visceral fat cells. Those cells carry more GH receptors than the fat stores under the skin [8,13].
- IGF-1 favors the burning of triglyceride, or stored fat, in the liver and the visceral depots [8,13].
- As GH breaks down fat, more free fatty acids flow to the liver. There, more of them are burned and fewer are turned back into stored fat. Liver triglyceride falls [13,17].
Across the main trials, VAT area on CT scans was about 15 to 18% lower at 26 weeks. Fat under the skin did not drop in a clinically meaningful way [5,6]. Cutting calories is different. It tends to lower both kinds of fat together.
What the studies found
The two Phase 3 trials in HIV
The Phase 3 program was two large trials at many sites. Both were double-blind and placebo-controlled. Both enrolled HIV-infected patients with fat buildup around the middle.
- Falutz and colleagues, 2007. The New England Journal of Medicine published this first trial. It randomized 412 patients for 26 weeks. They got placebo or 2 mg per day under the skin [5]. VAT was measured by CT at the L4-L5 level of the spine. It fell 15.2% with the drug and rose 5.0% with placebo. The treatment difference was minus 20.2% (p<0.001). Triglycerides improved significantly, and so did the ratio of total cholesterol to HDL. Adiponectin went up. In the treated group, IGF-1 rose 81% on average [5].
- Falutz and colleagues, 2010. This pooled analysis (Journal of Clinical Endocrinology & Metabolism) joined the two Phase 3 studies, with 806 people randomized, and the 26-week extension that followed. By week 26, the treatment effect on VAT against placebo was minus 15.4%. Patients who stayed on the drug kept the benefit through week 52. Patients moved onto placebo for the extension quickly moved back toward their baseline VAT. So the effect lasts only with continued dosing [6].
Safety over a longer period
Safety has been tracked for up to 52 weeks in the extension groups of the main trials [6]. A 2008 report by Falutz in AIDS covered the 26-week extension of the first trial [11].
- Side effects in 5% or more of subjects. Redness (erythema) and itching (pruritus) at the injection site. Joint pain (arthralgia). Swelling in the limbs (peripheral edema). Muscle pain (myalgia).
- Blood sugar needed watching. In the pooled Phase 3 data, fasting glucose rose in treated patients. The rise was modest but showed up in the statistics. HbA1c, a long-term blood sugar measure, went up by about 0.1 to 0.2 percentage points [6].
- Serious side effects were rare. The two groups had broadly similar rates.
- Type 2 diabetes. Clemmons and colleagues ran a separate randomized trial in 2017. It had 53 patients who had type 2 diabetes but not HIV. Blood sugar control did not get worse over 12 weeks on the drug. The study was sized to test safety, not benefit [15].
Liver fat and NAFLD
NAFLD is fatty liver disease not caused by alcohol. Stanley and colleagues ran two key trials.
- 2014, JAMA. The team randomized 50 HIV-infected adults with fat buildup around the middle. For 6 months they got the drug or placebo. A scan called proton MR spectroscopy measured liver fat. It fell by 2.0% in absolute terms with the drug and rose 0.9% with placebo, a net effect of minus 2.9% (p=0.003). VAT also fell, as expected [16].
- 2019, Lancet HIV. This larger trial followed 61 patients with HIV and fatty liver for 12 months, with a liver biopsy at the start and the end. Fatty liver meant a liver fat fraction of 5% or more. The drug significantly lowered liver fat. The effect against placebo was minus 4.1% in absolute terms, a relative drop of 37%. Under the microscope, liver scarring, called fibrosis, got worse in 10.5% of treated patients and 37.5% of placebo patients. Few randomized trials have shown a GHRH drug with a sign of slowing fibrosis in NAFLD, and this is one [17].
Stanley and Grinspoon reviewed how the drug works in 2015 (Growth Hormone & IGF Research). Their review places these results within the wider GH and IGF-1 system [8].
Thinking skills in HIV and aging
Observational studies have linked falling GH and IGF-1 to the decline in thinking skills with age. That link is why scientists looked here [18].
- Ellis and colleagues published a trial in 2025 (Journal of Infectious Diseases). They randomized 73 adults to the drug or to standard care. It was open label, with no placebo. All were HIV-positive with a suppressed virus and abdominal obesity. They scored a combined set of thinking and memory tests. Waist size went down as expected. The gap in test scores between the two groups was not statistically significant over the length of the trial [19].
- An earlier placebo-controlled trial by Baker and colleagues gave tesamorelin for 20 weeks to 152 older adults. Some had mild cognitive impairment and some were healthy. It reported a gain in executive function, the skills used to plan and focus. The Ellis trial in adults with HIV did not repeat that result [18,19].
Whether it helps thinking is still an open question.
Body composition outside HIV lipodystrophy
- Makimura and colleagues, 2014. They gave the drug or placebo for 12 months to 39 obese adults who made less GH than normal. IGF-1 rose more with the drug. Bigger rises in IGF-1 went with better phosphocreatine recovery on a 31P-MRS scan, a sign of how well muscle makes energy [20].
- Mangili and colleagues, 2015. They searched the pooled Phase 3 data for traits that predict who responds. Three stood out at 6 months: metabolic syndrome, high triglycerides and white race [21].
- Adrian and colleagues, 2019, Journal of Frailty & Aging. In Phase 3 patients with HIV whose VAT fell on treatment, the drug lowered fat inside muscle and raised muscle cross-sectional area. That points to a possible use in research on sarcopenia, the loss of muscle [22].
Blood fats, blood sugar and inflammation
Later substudies, and the pooled analysis of Phase 3, looked past VAT at wider metabolic effects [6].
- Triglycerides dropped by about 37 mg/dL, a treatment effect of about 12%.
- HDL improved in the first trial [5].
- The ratio of total cholesterol to HDL improved significantly. This ratio stands in for a pattern of blood fats that promotes artery plaque.
- Fasting glucose and HbA1c shifted by a modest but measurable amount.
In 2011, Stanley and colleagues reported in AIDS on blood markers tied to inflammation and clotting. These were CRP, adiponectin, tPA and PAI-1. tPA went down with the drug. Changes in tPA, PAI-1 and adiponectin tracked with VAT loss. That suggests the benefit comes with the loss of visceral fat [23].
Predicted heart risk
HIV-related lipodystrophy is itself a state of raised heart and blood vessel risk. So the changes in VAT and blood fats carry over into better forecast risk scores.
- In 2025, Grinspoon and colleagues went back to the Phase 3 data for a subanalysis. They found meaningful drops in 10-year risk scores for atherosclerotic cardiovascular disease (ASCVD). The combined changes in triglycerides, HDL and VAT drove the drops [24].
- McLaughlin and colleagues reported in 2023 that the benefits also reach today’s HIV patients on integrase strand transfer inhibitors (INSTIs). This group has shown more weight gain and more VAT gain on modern HIV drug regimens [25].
There are no data yet on hard outcomes such as major adverse cardiovascular events (MACE).
Safety
Few peptides that act on the GHRH system have a human safety record this large. The files behind the approvals by the FDA and Health Canada document over 1,000 subject-years of exposure in Phase 3 and its extensions [3,6,26].
Common side effects
These were reported in 5% or more of people in the main trials:
- Injection-site reactions. Redness, itching, bruising (hematoma) and rash. They were usually mild and cleared up without treatment [5,6].
- Joint and muscle pain. This fits with a more active GH system. People could generally tolerate it at the dose used [6].
- Swelling in the limbs. This makes sense, since GH causes the body to hold on to sodium [6].
- High blood sugar. Fasting glucose and HbA1c shifted by small but statistically significant amounts. The shift can matter clinically in people already prone to high blood sugar [6,15].
Known and possible risks
- IGF-1 above the normal range. The approved prescribing information advises IGF-1 tests from time to time. It says to pause dosing if levels pass the upper limit of normal. The reason is a theoretical risk of driving cell growth [3].
- Allergic reactions. Allergic-type reactions occurred in 3.6% of patients in the Phase 3 trials. They included itching, redness, flushing, hives and other rash [26].
- Fluid retention and carpal tunnel symptoms. These classic GH-type side effects were reported at low rates.
- Who is excluded. The label rules out use in pregnancy and in active cancer. It also rules out use when the link between the hypothalamus and pituitary is disrupted. Listed causes are pituitary removal, an underactive pituitary, a pituitary tumor, head trauma, and radiation to the head. Allergy to the drug or to mannitol also rules it out [26].
Outside HIV
Safety data in people without HIV come only from the trials above. Those are Clemmons 2017 in type 2 diabetes [15] and Makimura 2014 in obesity with low GH [20]. Stretching the findings past HIV-related lipodystrophy calls for caution.
Legal status in the US
- FDA approved for one use. Egrifta (tesamorelin for injection) won FDA approval in November 2010. The use is lowering abdominal fat in HIV-infected patients who have lipodystrophy and too much of that fat. Egrifta SV, a reformulated product that is simpler to mix, was approved in 2018 [3,26].
- Elsewhere. Health Canada approved it in 2014 for the same use [26]. The EMA and the MHRA have not approved it.
- Banned in sport. WADA bans it under class S2 at all times. That class names GHRH and its analogs directly [4].
- Research supply. When it is supplied for laboratory work, it comes under “for research use only” terms. It is not for use in people.
Limits of the research
- One narrow approved use. The Phase 3 evidence sits almost entirely in HIV-related lipodystrophy. Claims about healthy aging, obesity, or metabolic disease in general lean on small early trials that followed people only briefly [15,20,22].
- Stand-in measures. The approval, and most research since, was built on scan results (VAT, liver fat fraction) and blood markers (IGF-1, triglycerides, hsCRP). No trial has been sized to test hard outcomes such as MACE, new cases of diabetes or death from any cause.
- The effect fades after stopping. VAT comes back and IGF-1 returns to normal within weeks. So it is best described as a long-term treatment. On-and-off or cycled schedules have not been tested in well-controlled trials [6].
- The thinking-skills result is negative. There was a biological reason to expect a benefit. Still, the Ellis 2025 randomized trial did not show one in adults with HIV and abdominal obesity [19].
- Cost and access. Where it is approved, Egrifta has long ranked among the more costly HIV-related drugs. Use outside HIV clinics has been limited as a result.
- GH or IGF-1? The drug acts through both. Scientists cannot tell which one causes a given effect without extra clamp or knockout studies. Those have not been done in humans.
- Mostly North American data. Registry and post-marketing data come mainly from North America. That limits how well they apply to European study populations.
Tesamorelin has strong trial evidence for one thing: shrinking deep belly fat in people with HIV, for as long as they stay on it. Its other proposed uses are still unproven.
References
DOI-verified references. CrossRef lookups performed 2026-04-21.
- Ferdinandi ES, Brazeau P, High K, Procter B, Fennell S, Dubreuil P. Non-clinical pharmacology and safety evaluation of TH9507, a human growth hormone-releasing factor analogue. Basic Clin Pharmacol Toxicol. 2007;100(1):49–58. doi:10.1111/j.1742-7843.2007.00008.x
- Spooner LM, Olin JL. Tesamorelin: a growth hormone-releasing factor analogue for HIV-associated lipodystrophy. Ann Pharmacother. 2012;46(2):240–247. doi:10.1345/aph.1Q629
- Dhillon S. Tesamorelin: a review of its use in the management of HIV-associated lipodystrophy. Drugs. 2011;71(8):1071–1091. doi:10.2165/11202240-000000000-00000
- World Anti-Doping Agency. The World Anti-Doping Code International Standard: Prohibited List. Class S2 — Peptide Hormones, Growth Factors, Related Substances and Mimetics. WADA; updated annually.
- Falutz J, Allas S, Blot K, et al. Metabolic effects of a growth hormone-releasing factor in patients with HIV. N Engl J Med. 2007;357(23):2359–2370. doi:10.1056/NEJMoa072375
- Falutz J, Potvin D, Mamputu JC, et al. Effects of tesamorelin (TH9507), a growth hormone-releasing factor analog, in HIV-infected patients with excess abdominal fat: a pooled analysis of two multicenter, double-blind placebo-controlled phase 3 trials with safety extension data. J Clin Endocrinol Metab. 2010;95(9):4291–4304. doi:10.1210/jc.2010-0490
- Stanley TL, Grinspoon SK. GH/GHRH axis in HIV lipodystrophy. Pituitary. 2009;12(2):143–152. doi:10.1007/s11102-008-0092-8
- Stanley TL, Grinspoon SK. Effects of growth hormone-releasing hormone on visceral fat, metabolic, and cardiovascular indices in human studies. Growth Horm IGF Res. 2015;25(2):59–65. doi:10.1016/j.ghir.2014.12.005
- González-Sales M, Barrière O, Tremblay PO, et al. Population pharmacokinetic and pharmacodynamic analysis of tesamorelin in HIV-infected patients and healthy subjects. J Pharmacokinet Pharmacodyn. 2015;42(3):287–299. doi:10.1007/s10928-015-9416-2
- Brown LS Jr. The current state and future prospects of tesamorelin in managing HIV-associated lipodystrophy. Curr Opin Endocrinol Diabetes Obes. 2013;20(4):299–305.
- Falutz J, Allas S, Mamputu JC, et al. Long-term safety and effects of tesamorelin, a growth hormone-releasing factor analogue, in HIV patients with abdominal fat accumulation. AIDS. 2008;22(14):1719–1728. doi:10.1097/QAD.0b013e32830a5058
- Clarke BL, Khosla S. Growth hormone and bone: implications for adults with GH deficiency and the GH-IGF-1 axis. J Endocrinol Invest. 2011;34(6):456–470.
- Vijayakumar A, Yakar S, LeRoith D. The intricate role of growth hormone in metabolism. Front Endocrinol. 2011;2:32. doi:10.3389/fendo.2011.00032
- Møller N, Jørgensen JO. Effects of growth hormone on glucose, lipid, and protein metabolism in human subjects. Endocr Rev. 2009;30(2):152–177. doi:10.1210/er.2008-0027
- Clemmons DR, Miller S, Mamputu JC. Safety and metabolic effects of tesamorelin, a growth hormone-releasing factor analogue, in patients with type 2 diabetes: a randomized, placebo-controlled trial. PLoS One. 2017;12(6):e0179538. doi:10.1371/journal.pone.0179538
- Stanley TL, Feldpausch MN, Oh J, et al. Effect of tesamorelin on visceral fat and liver fat in HIV-infected patients with abdominal fat accumulation: a randomized clinical trial. JAMA. 2014;312(4):380–389. doi:10.1001/jama.2014.8334
- Stanley TL, Fourman LT, Feldpausch MN, et al. Effects of tesamorelin on non-alcoholic fatty liver disease in HIV: a randomised, double-blind, multicentre trial. Lancet HIV. 2019;6(12):e821–e830. doi:10.1016/S2352-3018(19)30338-8
- Baker LD, Barsness SM, Borson S, et al. Effects of growth hormone-releasing hormone on cognitive function in adults with mild cognitive impairment and healthy older adults: results of a controlled trial. Arch Neurol. 2012;69(11):1420–1429. doi:10.1001/archneurol.2012.1970
- Ellis RJ, Vaida F, Hu K, et al. Effects of tesamorelin on neurocognitive impairment in persons with HIV and abdominal obesity. J Infect Dis. 2025;231(5):1230–1238. doi:10.1093/infdis/jiaf012
- Makimura H, Murphy CA, Feldpausch MN, Grinspoon SK. The effects of tesamorelin on phosphocreatine recovery in obese subjects with reduced GH. J Clin Endocrinol Metab. 2014;99(1):338–343. doi:10.1210/jc.2013-3436
- Mangili A, Falutz J, Mamputu JC, Stepanians M, Hayward B. Predictors of treatment response to tesamorelin, a growth hormone-releasing factor analog, in HIV-infected patients with excess abdominal fat. PLoS One. 2015;10(10):e0140358. doi:10.1371/journal.pone.0140358
- Adrian S, Scherzinger A, Sanyal A, et al. The growth hormone releasing hormone analogue, tesamorelin, decreases muscle fat and increases muscle area in adults with HIV. J Frailty Aging. 2019;8(3):154–159. doi:10.14283/jfa.2018.45
- Stanley TL, Falutz J, Mamputu JC, Soulban G, Potvin D, Grinspoon SK. Effects of tesamorelin on inflammatory markers in HIV patients with excess abdominal fat: relationship with visceral adipose reduction. AIDS. 2011;25(10):1281–1288. doi:10.1097/QAD.0b013e328347f3f1
- Grinspoon SK, et al. Impact of tesamorelin on cardiovascular disease risk prediction scores in Phase 3 studies treatment arms: subanalysis. Open Forum Infect Dis. 2025. doi:10.1093/ofid/ofae631.633
- McLaughlin M, et al. Tesamorelin reduces visceral adipose tissue and liver fat in INSTI-treated persons with HIV. Open Forum Infect Dis. 2023. doi:10.1093/ofid/ofad500.1334
- US Food and Drug Administration. Egrifta (tesamorelin for injection) Prescribing Information. Theratechnologies Inc.; approved November 2010; Egrifta SV approved November 2018. Health Canada Notice of Compliance 2014.
- Bedimo R. Growth hormone and tesamorelin in the management of HIV-associated lipodystrophy. HIV AIDS (Auckl). 2011;3:69–79.
- Wang Y, Tomlinson B. Tesamorelin, a human growth hormone releasing factor analogue. Expert Opin Investig Drugs. 2009;18(3):303–310.
Related compounds
- CJC-1295 No DAC: Short-acting lab-made copy of GHRH, tested mostly in animals for pulses of growth hormone.
- Ipamorelin: Lab-made chain of five amino acids, tested mostly in animals for growth hormone release.
- Ipamorelin + CJC-1295: Two lab-made peptides that release growth hormone by different routes, studied as a pair.