KPV is a lab-made chain of three amino acids, copied from the tail end of a hormone called alpha-MSH. Scientists have tested it in cells and animals for calming inflammation, mostly in the gut. No human trial has been published.
In brief
- Since the early 1990s it has been tested as the shortest tail piece of α-MSH (positions 11 to 13) that keeps the hormone's effect against inflammation, without its pigment and wider hormone effects.
- In mice with colitis and in colon lining cells, scientists have tested how it enters gut cells through the PepT1 carrier and how it changes inflammation signals driven by NF-κB.
- It has been packed into swallowed nanoparticles aimed at the gut, and it builds on decades of cell and animal work on how α-MSH peptides affect inflammation signals in macrophages, neutrophils and lining cells.
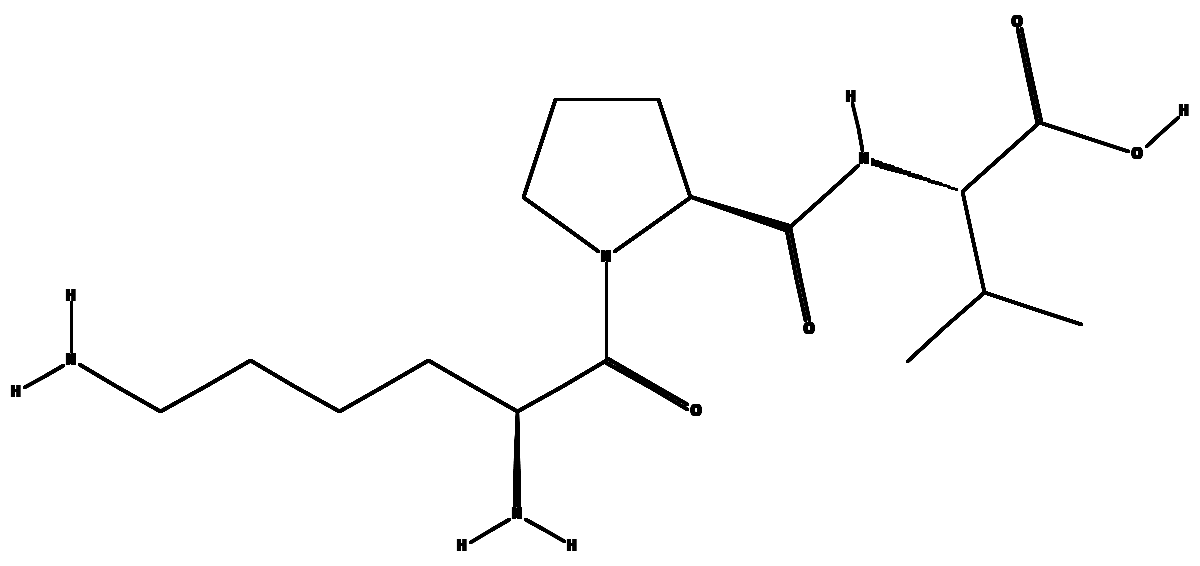
What KPV is
KPV is a lab-made peptide that has only been tested in cells and animals. As of 2026, the search for this guide found no published human trial. Most of the animal work is on gut inflammation in mice. This guide is for lab research and education only.
A peptide is a short chain of amino acids, the building blocks of protein. KPV has three: lysine, proline and valine. The name comes from their one-letter codes.
Those three amino acids are the tail end of a natural hormone called alpha-MSH, written α-MSH. The full name is alpha-melanocyte-stimulating hormone. It is 13 amino acids long and is cut from a larger parent protein called POMC. KPV matches positions 11 to 13.
Why study such a small piece? KPV is the shortest part of α-MSH reported to keep a real effect against inflammation in animal and cell tests. It does this without the hormone’s effect on skin pigment or its wider hormone effects [14].
Interest in this tail end goes back to the early 1990s. Scientists made variants of the piece at positions 11 to 13 and changed the 3D arrangement of their atoms to see how that altered the strength of the effect. That work made the tail a research subject of its own, apart from what the parent hormone does for pigment and the hormone system [2].
Later studies tested KPV itself, not just α-MSH. One found that cells lining the gut pull KPV inside through a carrier called PepT1, and that this went with lower signs of inflammation in mice with colitis [15]. Colitis is inflammation of the colon. Another tested KPV in several mouse models of inflammatory bowel disease [16].
How much research there is
A small set of cell and animal studies on KPV, a larger set on its parent hormone, and nothing in people.
| Question | Answer |
|---|---|
| Stage | Cells and animals only. No published human trial was found |
| Kinds of study | Tests on cells in a dish (colon lining cells, monocytes, glioma cells) and tests in live rodents (colitis, contact sensitivity, cytokine challenge) |
| People studied | None. Every study found used cells or animals |
| Checked by other labs | For α-MSH, yes. Separate groups reported the NF-κB block over the years [6], [7], [8]. For KPV itself, only in part. Two groups ran the gut studies [15], [16], and few outside labs have repeated them |
| Where the work comes from | Gut studies of KPV itself come from two circles of scientists, one in Atlanta and one in Münster, Germany. Work on how α-MSH acts is spread more widely, but it is not about KPV |
| Longest study | Short rodent studies, lasting days to a few weeks |
| Approval | Experimental research compound. No approval from the FDA, the EMA or the MHRA was found |
| Do the results agree | Blocking of NF-κB has been reported again and again since the late 1990s, in different cell types and by different groups. The smaller set of KPV gut studies also agree with each other |
How it might work
Cell and animal studies point to three linked ideas. KPV may block a protein called NF-κB. Gut cells may carry it inside. And it may change how some immune cells behave.
One caution applies to this whole section. Much of the basic work used α-MSH or close relatives of it, not KPV alone. Where a study used KPV itself, the text says so.
Blocking NF-κB
NF-κB, short for nuclear factor kappa B, is a protein that turns genes on. It sits at the center of the body’s inflammation response. Many studies have tested whether α-MSH and its three-part relatives can block it.
- In cells. Early work found that α-MSH stopped NF-κB from switching on in cultured cells. The triggers were a range of inflammation-causing agents, including one called TNF-α [6].
- Sticky molecules. In a related dish study, α-MSH held back adhesion molecules, which help immune cells stick. Cytokines, the signal proteins of the immune system, normally raise them. The effect ran through NF-κB [7].
- Brain inflammation. α-MSH peptides given to the whole body blocked NF-κB in animals with lab-induced brain inflammation [8].
- Human glioma cells. A partner study found the same block in these brain tumor cells. It also found that IκBα, a protein that holds NF-κB in check, was no longer broken down [9].
One study came closer to KPV. It used GKPV, which covers positions 10 to 13 of α-MSH. This four-part piece is just one amino acid longer than KPV. The peptide was fixed to a surface. In a dish, it lowered NF-κB activity that TNF-α had switched on. That supports the idea that this tail of α-MSH can act on NF-κB without the rest of the hormone [13].
Getting into gut cells
This finding is about KPV itself. PepT1, or peptide transporter 1, is a carrier that moves short peptides. It sits on the gut-facing surface of the cells that line the intestine. KPV is one of the things PepT1 carries.
In mice, KPV taken up this way went with less gut inflammation. The authors proposed PepT1 as a way for small peptides like KPV to act right inside gut lining tissue [15].
Scientists in the same field also studied the carrier alone. In mice, too much PepT1 changed how easily colitis could be set off. The path involved NOD2, a receptor of the body’s first-line immune system. That helps explain why researchers care about the PepT1 route in gut inflammation [19].
Wider immune effects
Older studies looked at how α-MSH and its relatives change immune cells in general.
- Macrophages are immune cells that make nitric oxide using an enzyme. One study found signs that α-MSH, made by these cells, tunes that enzyme in the same cells [4].
- Neutrophils are another immune cell. They carry specific receptors for α-MSH. In a dish, α-MSH cut their movement toward chemical signals [5].
- In animals, α-MSH relatives blocked inflammation in outer body tissue that was set off by a signal called IL-1β [3].
A later review pulled this work together. It described α-MSH as a neuroimmunomodulator, a nerve-related molecule that adjusts the immune system [10].
Does it need a receptor?
α-MSH is thought to act mainly through melanocortin receptors, above all one named MC1R. A receptor is the spot on a cell where a molecule attaches.
KPV and similar tail pieces grip those classic receptors far more weakly than the whole hormone does. Yet in some test systems they still worked against inflammation. So scientists have proposed that part of the effect does not need a receptor at all. A direct effect on NF-κB is one example. The classic receptor routes may work alongside it [17].
A broad drug review on targeting melanocortin receptors placed the three-part peptide work within the wider field. It noted that how much each short piece depends on a receptor is still being studied [12].
What the studies found
Few published studies are about KPV itself. They focus on gut and skin inflammation. Behind them are decades of wider work on α-MSH and related pieces.
Gut and colitis
- The main gut study. KPV entered cells through PepT1. In mice with colitis, that went with lower signs of gut inflammation [15].
- Bowel disease models. A second study tested KPV in several mouse models of inflammatory bowel disease. It reported that the peptide could work against inflammation there [16].
- Early background. A report published as a conference abstract tested α-MSH on colon lining cells in a dish. Cytokines make those cells release interleukin-8, and α-MSH changed that release. It gave an early hint that this peptide family acts on gut lining cells, before the KPV studies came out [11].
- Oral delivery. Newer work packed KPV into nanoparticles coated with hyaluronic acid. The particles were swallowed and aimed at the gut. In mice with ulcerative colitis, signs of disease activity dropped. That project was about engineering a delivery method, not about how KPV alone acts as a drug [20].
- The carrier. Work on PepT1, done apart from KPV, linked the carrier to colitis risk through a path that depends on NOD2. That is why this entry route matters to gut researchers [19].
Skin
- Early animal work found that α-MSH peptides blocked sudden inflammation and contact sensitivity. This was part of the wider work on structure and effect that later narrowed to the three-part tail [1].
- A later review summed up the animal and cell evidence that α-MSH works against inflammation in skin. It discussed what this peptide family might mean for future skin research [18].
Immune system in general
- Studies across the 1990s reported that α-MSH and its relatives affected nitric oxide made by macrophages [4], the movement of neutrophils [5], and outer tissue inflammation set off by IL-1β [3]. The later gut and skin studies of KPV grew out of this background.
- Two linked studies from one group found that α-MSH peptides given to the whole body blocked NF-κB in models of brain inflammation. One of them included human glioma cells [8], [9].
Safety
In cells and animals
- The animal studies reviewed here reported no serious harm from KPV or close three-part α-MSH relatives [15], [16].
- In the nanoparticle study, treated animals had lower signs of colitis tissue damage than untreated ones. The paper described no new safety problems caused by the peptide [20].
- Dish studies and brain inflammation studies of α-MSH peptides reported no cell-killing effect at the strengths tested [8], [9].
What is not known
- No published human trial data on KPV was found. How the human body handles it, what doses do, and long-term safety have not been set out in peer-reviewed papers.
- Most KPV results come from a few groups using gut inflammation and delivery models. Nobody has directly studied the safety of KPV itself on skin or given to the whole body. That work exists only for the parent hormone.
- It is not settled how much of the effect comes through melanocortin receptors and how much comes from blocking NF-κB without a receptor. That makes it hard to judge safety from the way the compound works [17].
- No formal drug interaction study of KPV was found.
Legal status in the US
- Not FDA approved. KPV is not approved by the FDA for any use. The same is true of the EMA in Europe and the MHRA in the UK.
- Sport. The current World Anti-Doping Agency (WADA) Prohibited List does not name KPV. It does not name its parent hormone, α-MSH, either. Class S0 of the list bans drug-like substances that no government health authority has approved for treating people, even when the list does not name them.
- Research use. It is supplied strictly for laboratory research, not for human use or use in competition.
Limits of the research
- No human trials. Everything in this guide comes from cells in a dish or from animals. If human studies are ever done, the effects and the safety picture may turn out different.
- Few studies used KPV itself. Much of the evidence on how it works is about α-MSH or close relatives, including the four-part piece GKPV. That background is not the same as direct data on KPV.
- A small circle of labs. The KPV gut and delivery studies come from two circles of scientists. Few outside groups have repeated them.
- Mixed models and routes. The studies include dish tests, whole-body dosing in rodents and experimental swallowed nanoparticles. A result from one model or route may not hold in another.
- Short studies only. The longest treatments reported were short rodent studies. Nothing is known from published papers about longer periods.
- The mechanism is not pinned down. How much comes from classic melanocortin receptors and how much from receptor-free blocking of NF-κB is still an open question.
- Missing negative results. As with any narrow field that spans decades, bias in what gets published or reported cannot be ruled out.
KPV has calmed inflammation in cells and in mice. No published study has tested it in people.
References
Selected peer-reviewed references, each verified against the CrossRef API before inclusion. Ordered by date of publication.
- Hiltz M, Lipton J (1990). Alpha-MSH peptides inhibit acute inflammation and contact sensitivity. Peptides, 11(5), 979–982. DOI: 10.1016/0196-9781(90)90020-6
- Hiltz M, Catania A, Lipton J (1991). Anti-inflammatory activity of α-MSH(11–13) analogs: Influences of alteration in stereochemistry. Peptides, 12(4), 767–771. DOI: 10.1016/0196-9781(91)90131-8
- Watanabe T, Hiltz M, Catania A, Lipton J (1993). Inhibition of IL-1β-induced peripheral inflammation by peripheral and central administration of analogs of the neuropeptide α-MSH. Brain Research Bulletin, 32(3), 311–314. DOI: 10.1016/0361-9230(93)90192-e
- Star R, Rajora N, Huang J, Stock R, et al. (1995). Evidence of autocrine modulation of macrophage nitric oxide synthase by alpha-melanocyte-stimulating hormone. Proceedings of the National Academy of Sciences, 92(17), 8016–8020. DOI: 10.1073/pnas.92.17.8016
- Catania A, Rajora N, Capsoni F, Minonzio F, et al. (1996). The neuropeptide α-MSH has specific receptors on neutrophils and reduces chemotaxis in vitro. Peptides, 17(4), 675–679. DOI: 10.1016/0196-9781(96)00037-x
- Manna S, Aggarwal B (1998). α-Melanocyte-Stimulating Hormone Inhibits the Nuclear Transcription Factor NF-κB Activation Induced by Various Inflammatory Agents. The Journal of Immunology, 161(6), 2873–2880. DOI: 10.4049/jimmunol.161.6.2873
- Kalden D, Scholzen T, Brzoska T, Luger T (1999). Mechanisms of the Antiinflammatory Effects of α-MSH: Role of Transcription Factor NF-κB and Adhesion Molecule Expression. Annals of the New York Academy of Sciences, 885(1), 254–261. DOI: 10.1111/j.1749-6632.1999.tb08682.x
- Ichiyama T, Sakai T, Catania A, Barsh G, et al. (1999). Systemically administered α-melanocyte-stimulating peptides inhibit NF-κB activation in experimental brain inflammation. Brain Research, 836(1-2), 31–37. DOI: 10.1016/s0006-8993(99)01584-x
- Ichiyama T, Zhao H, Catania A, Furukawa S, et al. (1999). α-Melanocyte-Stimulating Hormone Inhibits NF-κB Activation and IκBα Degradation in Human Glioma Cells and in Experimental Brain Inflammation. Experimental Neurology, 157(2), 359–365. DOI: 10.1006/exnr.1999.7064
- Lipton J, Catania A, Ichiyama T (2000). Marshaling the Anti-Inflammatory Influence of the Neuroimmunomodulator α-MSH. Physiology, 15(4), 192–195. DOI: 10.1152/physiologyonline.2000.15.4.192
- Johenning H, Maaser C, Heidemann J, Brzoska T, et al. (2003). Modulation of cytokine-induced interleukin (IL)-8 secretion in colonic epithelial cells in vitro by alpha-melanocyte-stimulating hormone (MSH). Gastroenterology, 124(4), A158. DOI: 10.1016/s0016-5085(03)80786-2
- Catania A, Gatti S, Colombo G, Lipton J (2004). Targeting Melanocortin Receptors as a Novel Strategy to Control Inflammation. Pharmacological Reviews, 56(1), 1–29. DOI: 10.1124/pr.56.1.1
- Kelly J, Moir A, Carlson K, Yang Y, et al. (2006). Immobilized α-melanocyte stimulating hormone 10–13 (GKPV) inhibits tumor necrosis factor-α stimulated NF-κB activity. Peptides, 27(2), 431–437. DOI: 10.1016/j.peptides.2005.03.062
- Luger T, Brzoska T (2007). α-MSH related peptides: a new class of anti-inflammatory and immunomodulating drugs. Annals of the Rheumatic Diseases, 66, iii52–iii55. DOI: 10.1136/ard.2007.079780
- Dalmasso G, Charrier-Hisamuddin L, Thu Nguyen H, Yan Y, et al. (2008). PepT1-Mediated Tripeptide KPV Uptake Reduces Intestinal Inflammation. Gastroenterology, 134(1), 166–178. DOI: 10.1053/j.gastro.2007.10.026
- Kannengiesser K, Maaser C, Heidemann J, Luegering A, et al. (2008). Melanocortin-derived tripeptide KPV has anti-inflammatory potential in murine models of inflammatory bowel disease. Inflammatory Bowel Diseases, 14(3), 324–331. DOI: 10.1002/ibd.20334
- Brzoska T, Luger T, Maaser C, Abels C, et al. (2008). α-Melanocyte-Stimulating Hormone and Related Tripeptides: Biochemistry, Antiinflammatory and Protective Effects in Vitro and in Vivo, and Future Perspectives for the Treatment of Immune-Mediated Inflammatory Diseases. Endocrine Reviews, 29(5), 581–602. DOI: 10.1210/er.2007-0027
- Auriemma M, Luger T, Loser K, Amerio P, et al. (2009). The Antiinflammatory Effect of Alpha-MSH in Skin: A Promise for New Treatment Strategies. Anti-Inflammatory & Anti-Allergy Agents in Medicinal Chemistry, 8(1), 14–21. DOI: 10.2174/187152309787580801
- Dalmasso G, Nguyen H, Ingersoll S, Ayyadurai S, et al. (2011). The PepT1–NOD2 Signaling Pathway Aggravates Induced Colitis in Mice. Gastroenterology, 141(4), 1334–1345. DOI: 10.1053/j.gastro.2011.06.080
- Xiao B, Xu Z, Viennois E, Zhang Y, et al. (2017). Orally Targeted Delivery of Tripeptide KPV via Hyaluronic Acid-Functionalized Nanoparticles Efficiently Alleviates Ulcerative Colitis. Molecular Therapy, 25(7), 1628–1640. DOI: 10.1016/j.ymthe.2016.11.020
Related compounds
- BPC-157: Lab-made chain of 15 amino acids, tested in animals for blood vessel growth and tissue repair.
- Thymosin Alpha-1: Immune peptide from the thymus, sold as an approved drug in many countries.
- GHK-Cu: Copper-bound chain of three amino acids, tested in cells and animals for skin and wound repair.