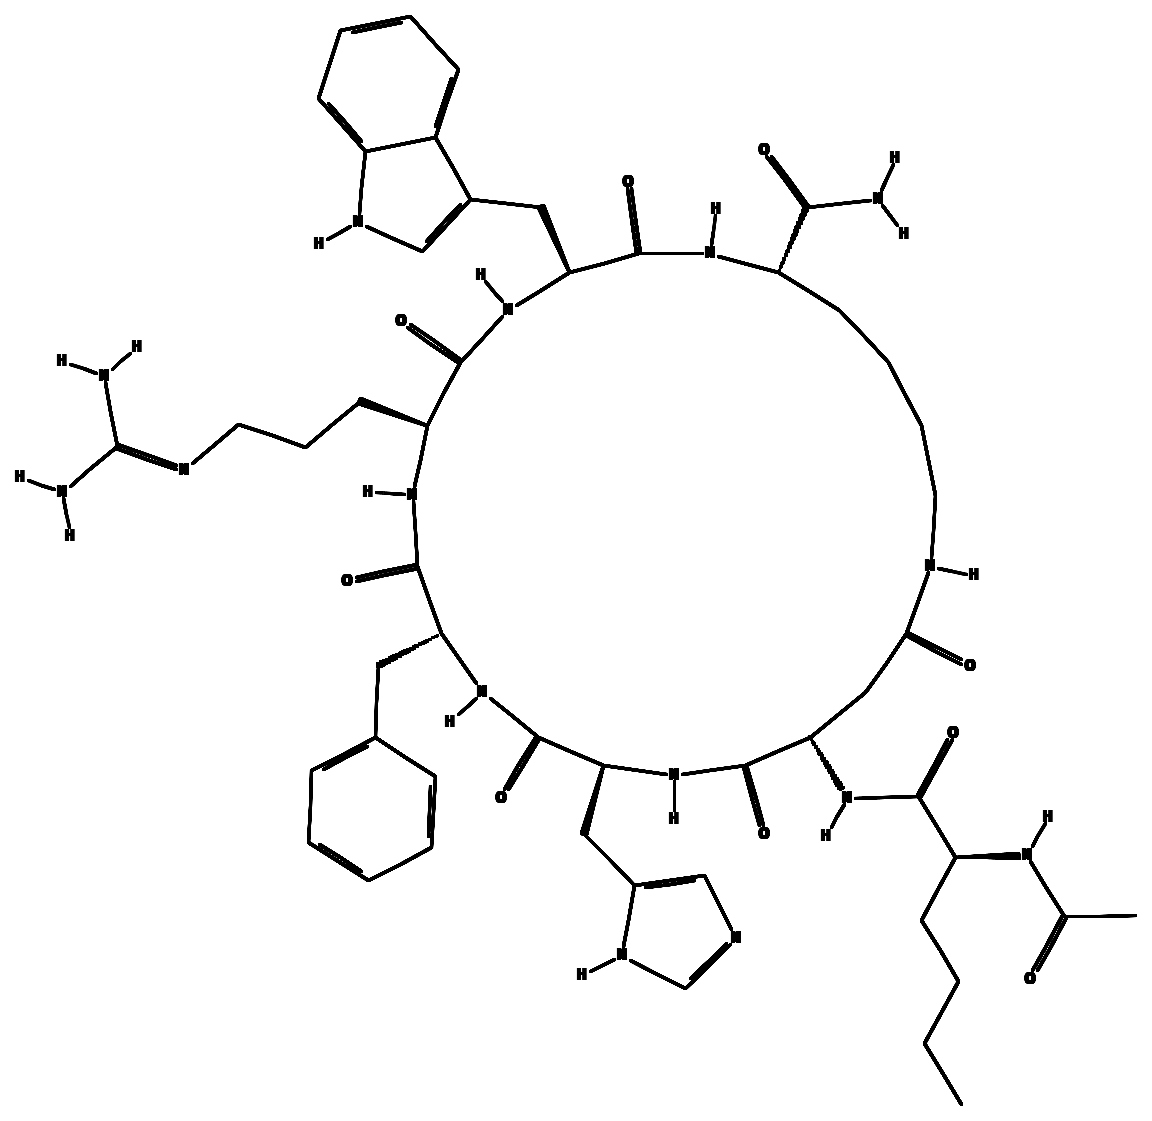
Melanotan 2 is a lab-made ring of seven amino acids, built at the University of Arizona to copy a natural skin-darkening hormone. It was tested in a few small human studies and never approved. Doctors have reported melanoma and blood vessel harms in people who injected it.
In brief
- It switches on four receptors at once: MC1R, MC3R, MC4R and MC5R. MC1R makes skin produce pigment. MC3R and MC4R act in the brain on eating and sexual arousal.
- It came before PT-141 (bremelanotide), a compound aimed more narrowly at the brain. The FDA later approved PT-141 for low sexual desire in women who have not reached menopause.
- People who used it without approval have had recorded harms: case reports of melanoma and erupting moles, kidney infarction, and a steady pattern of gut, heart and blood vessel side effects.
What Melanotan 2 is
Melanotan 2 is a lab-made peptide that was tested in a handful of small human studies between 1996 and 2000. No large trial has been published. No drug agency has approved it, and doctors have published reports of serious harm in people who injected it on their own.
A peptide is a short chain of amino acids, the building blocks of protein. Melanotan 2 has seven of them joined in a ring. Some papers call it MT-II, others MT-2. It copies a natural hormone called alpha-melanocyte-stimulating hormone, or α-MSH. The body breaks down natural α-MSH fast. The ring shape of Melanotan 2 resists that and makes it last far longer, which is why labs find it handy for studying melanocortin receptors [1], [2]. A receptor is a docking site on a cell.
Two University of Arizona research groups made it in the late 1980s. One was led by Professor Mac E. Hadley. Dr Robert T. Dorr led the other. They wanted a drug that could help prevent skin cancer, an approach called “chemoprevention”. The plan was to make skin produce more pigment, so it would be shielded from the sun with no need for UV light [3].
Melanotan 2 is not picky. It attaches to four melanocortin receptors (MC1R, MC3R, MC4R, MC5R) about equally well, and switches all of them on [1]. That wide reach explains the mix of effects seen in early lab studies: darker skin, less appetite, sexual arousal and more active oil glands. It also explains the side effects.
No recognized regulator has approved it for use in people. The FDA, EMA, MHRA and TGA have never cleared it for sale, and it has no accepted medical use. A later compound from the same chemistry work, bremelanotide (PT-141), acts more narrowly on the brain. The FDA went on to approve that one for hypoactive sexual desire disorder (HSDD), a lasting lack of sexual desire, in women who have not reached menopause. Melanotan 2 stayed a research compound. Even so, online sellers have offered it since the late 2000s. People inject it to get a cosmetic “tan”. This consumer market has no approval at all [12], [13], [14].
Only published research is covered in this guide. It does not endorse injecting it and does not discuss doses for people.
How much research there is
The record is unusual. The early lab work and the first human pilot were well done. But the compound never entered a controlled drug development program. Most of the later human writing is safety reporting about people who used it without approval.
| Question | Answer |
|---|---|
| Published studies | About 60 or more. They span receptor science, phase I results, and case reports. This guide cites 14 key ones |
| Randomized controlled trials | One small crossover trial with a placebo control, in 10 men with psychogenic erectile dysfunction (Wessells 1998). Phase II and III trials: none, for any use |
| Approval | None from the FDA, EMA, MHRA or TGA. The later compound PT-141 (bremelanotide) is FDA approved for HSDD. Melanotan 2 is not |
| Safety signals on record | Melanoma, and moles that erupt or darken (Hjuler 2014, Schulze 2014). Kidney infarction (Peters 2020). Gut and heart or blood vessel events (Habbema 2017). Several separate skin research groups report the same signals |
| Quality of unregulated product | LC-MS lab tests of product bought online found uneven purity, impurities and the wrong amount of peptide (Breindahl 2015) |
How it works
Everything Melanotan 2 does comes from the melanocortin receptors. Because it hits several at once, both the hoped-for effects and the human safety signals have to be read with that in mind.
The melanocortin receptors
There are five of these receptors, MC1R to MC5R. All are G-protein-coupled receptors. They signal mainly through a protein called Gs and a messenger called cyclic AMP. The body’s own keys for them are cut from one parent protein, proopiomelanocortin (POMC). Those keys are ACTH and three forms of MSH: α-MSH, β-MSH and γ-MSH [1].
Each receptor sits in different tissue and has its own job:
- MC1R is found mostly on melanocytes (pigment cells) and on white blood cells.
- MC2R is the receptor for ACTH in the adrenal glands.
- MC3R and MC4R are on nerve cells in the hypothalamus and limbic areas of the brain. Those cells deal with energy balance and sexual behavior.
- MC5R is on the skin’s oil glands and is also found in skeletal muscle.
Scientists built Melanotan 2 on purpose as a “superpotent” ring-shaped copy of α-MSH. Its grip on MC1R, MC3R, MC4R, MC5R is tighter than the natural hormone’s by between one and two orders of magnitude. That means 10 to 100 times. At levels found in the body, it does not turn on MC2R in any real way [2].
Four receptors fire at the same moment. So anything seen in a living animal or person is the sum of four pathways, not one clean effect.
MC1R and skin color
Skin darkening is the best known research effect, and MC1R is the main receptor behind it. The process of making pigment is called melanogenesis. The steps go like this:
- Melanotan 2 switches on MC1R on melanocytes in the outer skin.
- Cyclic AMP rises inside the cell.
- That raises MITF (microphthalmia-associated transcription factor), a protein that controls pigment genes.
- MITF raises the pigment-making enzymes tyrosinase, TRP-1 and TRP-2.
In the end, the cell makes less of the lighter pigment, pheomelanin, and more of the darker one, eumelanin. Total melanin in the outer skin goes up [3], [4].
In early human studies in Arizona, healthy men got injections under the skin, and their skin darkened over the next few weeks. This was shown first with Melanotan 1 [4] and then with Melanotan 2 [3].
The first idea was that drug-made eumelanin might shield DNA from UV damage. Controlled trials never confirmed that cancer prevention idea. The program did not move on to the large studies that would test whether it worked.
MC3R and MC4R in the brain
These two receptors are found in the hypothalamus, the limbic system and the brainstem. They are central controls for eating, energy use and sexual arousal. In animal and lab models, turning on MC4R above all cut food intake and raised sexual arousal. That finding is what later led to bremelanotide (PT-141), a compound aimed more narrowly at the brain and built for HSDD [5], [6], [7].
In human studies of Melanotan 2, the MC3R and MC4R effects showed up as:
- erections that came on by themselves
- more sexual desire, as reported by the men
- less appetite
- nausea
These turned up again and again in Arizona’s phase I study and in the erection studies. No dose could separate them from the skin darkening. That follows directly from the compound hitting every receptor at once [3], [5], [6].
MC5R and the skin’s oil glands
MC5R is on oil glands, other glands that release fluids, and skeletal muscle. Turning it on raises the output of sebum, the skin’s oil. In rodents it has also been tied to body heat control and gland responses [1].
People who used the compound without approval have reported oilier faces and acne-like flares. This pathway probably plays a part. No forward-looking human study has formally measured it.
What the studies found
The published work falls into four phases:
- the first Arizona skin pigment program, from the late 1980s through the 1990s
- the erection studies that gave rise to the PT-141 program, from the late 1990s to 2000
- case reports and drug safety reports on harm from unapproved consumer use, from 2009 to 2020
- a smaller set of lab papers describing the unregulated supply chain
Early skin darkening work
- The 1991 tanning study in people. Levine and colleagues published the first controlled proof that a lab-made melanotropin, injected under the skin, could darken healthy men. The compound was Melanotan 1, the straight-chain relative, not Melanotan 2. The trial was randomized and double-blind. It had 28 men, who got ten injections of the peptide or salt water over 12 days. Skin color was measured with an instrument. The men on the peptide got darker, and the men on placebo did not [4]. The study appeared in JAMA and was the proof of concept for the Melanotan program.
- Stability work, 1994. Lan, Ugwu and colleagues described the chemical and physical traits of Melanotan 2. They also tested how stable it is in solution and how it behaves before being made into a product. That lab groundwork made later clinical-grade studies possible [2].
- Melanotan 1 compared. Melanotan 1, also called afamelanotide, is a straight-chain relative. Later Arizona work set it side by side with the ring-shaped Melanotan 2. The two differed in how strongly they darkened skin and in how the body handled them [3]. Melanotan 1 went down its own path and won limited approval, under the name Scenesse, for a disease called erythropoietic protoporphyria. Melanotan 2 never got that far.
The 1996 phase I study
The key record of human exposure is the phase I study from Arizona that Dorr and colleagues published in 1996 [3]. It was a small pilot in three healthy male volunteers. It was single-blind. The men got Melanotan 2 on some days and salt water on others, as injections under the skin in rising doses. The main results:
- Two of the three men had darker skin a week after dosing ended. This matched what had been seen earlier with Melanotan 1 tanning, now with a ring-shaped version [3].
- Side effects capped the dose. They included nausea, vomiting, a flushed face, reflex stretching and yawning, and, at higher doses, erections that came on by themselves.
- The men kept reporting less appetite. That fits an MC4R effect on the feeding circuits of the hypothalamus.
- The study did not measure cancer prevention or long-term safety. It was plainly a short pilot.
This 1996 paper is still the fullest forward-looking human dataset on the compound. No indexed journal has published a phase II trial, a phase III trial or any large controlled trial of it. The compound never moved toward a filing with regulators.
Erection studies that led to PT-141
The erections seen in that phase I study were an unplanned finding. They set off a separate line of research on erections driven by melanocortin receptors. That line ended up seeding PT-141.
- 1998, psychogenic erectile dysfunction. Wessells, Hadley, Dorr and colleagues studied men whose erection problems had a psychological cause. The study was double-blind with a placebo control, and each man crossed over between the two. Melanotan 2 injected under the skin started erections, and placebo did not match it [5].
- 2000, organic erectile dysfunction. The next trial enrolled men whose erection problems had a physical cause. It reported that an α-MSH analogue, which was Melanotan 2, improved their erections and their own rating of sexual desire [6].
- 2000, a review of the human data. Wessells and colleagues summed up the human results with melanocortin receptor agonists up to then. An agonist is a compound that switches a receptor on. They credited the erection and motivation effects to MC3R and MC4R. They also made the case for compounds aimed more narrowly at the brain. That program turned into bremelanotide [7].
Today the FDA lists bremelanotide as an approved drug for HSDD, and a separate guide covers it. Melanotan 2 never went down that road. Because it hits so many receptors, it caused off-target effects that were judged unacceptable: skin darkening, nausea and darkening of moles.
Harms reported in users
Since about 2008, a large stack of case reports and drug safety reports has described harm in people who used Melanotan 2 from unregulated sellers. The signals are consistent. They come from several separate skin research groups in several countries. They cannot be waved away as one-off oddities.
- Moles that erupt or darken. A nevus (plural nevi) is a mole. In 2014, Schulze and colleagues reported new nevi erupting, and existing nevi darkening, within 24 hours of just one dose. This shows how fast the compound can switch on melanocytes all over the skin, including those inside moles and not only those in the outer skin [10].
- Melanoma. In 2014, Hjuler and Lorentzen described a skin melanoma in a patient whose Melanotan 2 use was on record. They pointed directly to the cancer worry. In theory, a compound that stirs up every melanocortin receptor could also stir up melanocytes that have already turned abnormal [9]. More scattered reports have followed, of abnormal (dysplastic) nevi, odd pigment patterns and melanoma among people using Melanotan.
- Kidney and blood vessel events. In 2020, Peters and colleagues reported a kidney infarction, which is tissue death from a blocked blood supply, linked to Melanotan 2 use. They also reviewed earlier papers. They named a believable cause, the effect of melanocortin agonists on blood vessels. They also stressed that the compound could bring on serious heart and blood vessel events [11].
- A structured safety review. In 2017, Habbema and colleagues reviewed the risks of unregulated use of α-MSH analogues. They pulled together case reports on melanoma, atypical nevi and gut symptoms. The list also had heart and blood vessel events, with heart attack and kidney infarction among them. It ended with priapism, an erection that will not go down, and reactions where the needle went in [8]. Their verdict: the harms in print are consistent and matter clinically. They said nobody should use the compound outside controlled research.
- More published harms. Langan and colleagues summed up the wider skin medicine literature. They framed the use of Melanotan as a concern for public health and not just a cosmetic matter [13].
To be plain: the bulk of the published evidence points to a real cancer and heart safety signal, not a mere cosmetic nuisance. Lab research on Melanotan 2 in cells or animals has to take these papers into account.
Warnings and product quality
- Use among the public. In 2009, Evans-Brown and colleagues described how widely Melanotan I and II were used among the general public in the UK, through gyms and the internet. They called for regulators to act [12].
- The FDA’s position. Melanotan 2 has no FDA approval for any use. It has warned consumers against tanning products that are injected. It has also acted against sellers who sell it as a cosmetic product.
- What is in the vial. In 2015, Breindahl and colleagues bought Melanotan 2 products from internet sellers and tested them with a lab method called LC-UV-MS/MS. A large share of samples had uneven purity, the wrong amount of peptide, or impurities [14]. This matters when reading reports of harm. Problems blamed on “Melanotan 2” may come partly from contaminants or wrongly identified peptides, and not only from the intended ingredient.
Safety
Whether people inject the compound is outside the scope of this guide, which takes no side on it. These are the main concerns on record:
- Melanoma and abnormal moles. Melanoma and atypical nevi turn up in several separate case reports on people who used Melanotan 2 [9], [10]. The biology makes this highly believable. The compound switches on MC1R without any targeting, including in melanocytes that are abnormal or already cancerous.
- Heart and blood vessel events. Kidney infarction, heart events and priapism all appear in the drug safety literature [8], [11].
- Gut effects. Nausea, vomiting and a flushed face show up steadily. They appear in the phase I data from Arizona and again in case series of people who used it without approval [3], [8].
- Identity and purity. Lab surveys of Melanotan 2 bought online found big swings in how pure it was and how much peptide it held [14]. Research with material that is not made to an official drug standard depends on separately confirmed lab data from HPLC and LC-MS. It also needs a Certificate of Analysis for that specific compound.
Legal status in the US
- Not FDA approved. The FDA has never approved it for any use. The same goes for the EMA in Europe, the MHRA in the UK and the TGA.
- FDA action. Sellers that market it as a supplement or a cosmetic have faced FDA enforcement.
- Banned in sport. Under the World Anti-Doping Agency Prohibited List it counts as a non-approved substance (class S0). Competitive athletes are barred from it at all times.
Limits of the research
- No large trials. The big controlled trials needed for approval were never run. The human data are small pilot studies plus case reports from doctors. That falls short of modern standards for proving a drug works or is safe.
- Long-term safety unknown. Long-term safety, cancer risk and harm to reproduction have not been properly measured in people. The published worries make biological sense, but no forward-looking controlled data back them.
- Uncertain product. Many harm reports involve unregulated product whose identity is unclear. That makes it hard to pin the cause on Melanotan 2 itself and not on contaminants or mislabeled peptides [14].
- Sexual response data are narrow. They come from small studies of erections in men. Nothing comparable exists for women. For that research question, the later brain-targeted compound PT-141 has replaced Melanotan 2.
A few small studies show Melanotan 2 darkens skin and affects appetite and arousal in men. No large trial has tested it, and the reports of harm are consistent.
References
Selected peer-reviewed references. Ordered by relevance to this guide.
- Hadley ME, Haskell-Luevano C. The proopiomelanocortin system. Annals of the New York Academy of Sciences. 1999;885:1–21. PMID: 10816638
- Lan EL, Ugwu SO, Blanchard J, Fang X, Hruby VJ, Sharma S. Preformulation studies with melanotan-II: a potential skin cancer chemopreventive peptide. Journal of Pharmaceutical Sciences. 1994;83(8):1081–1084. PMID: 7983590
- Dorr RT, Lines R, Levine N, Brooks C, Xiang L, Hruby VJ, Hadley ME. Evaluation of melanotan-II, a superpotent cyclic melanotropic peptide in a pilot phase-I clinical study. Life Sciences. 1996;58(20):1777–1784. PMID: 8637402
- Levine N, Sheftel SN, Eytan T, Dorr RT, Hadley ME, Weinrach JC, Ertl GA, Toth K, McGee DL, Hruby VJ. Induction of skin tanning by subcutaneous administration of a potent synthetic melanotropin. JAMA. 1991;266(19):2730–2736. PMID: 1658407
- Wessells H, Fuciarelli K, Hansen J, Hadley ME, Hruby VJ, Dorr R, Levine N. Synthetic melanotropic peptide initiates erections in men with psychogenic erectile dysfunction: double-blind, placebo controlled crossover study. The Journal of Urology. 1998;160(2):389–393. PMID: 9679884
- Wessells H, Gralnek D, Dorr R, Hruby VJ, Hadley ME, Levine N. Effect of an alpha-melanocyte stimulating hormone analog on penile erection and sexual desire in men with organic erectile dysfunction. Urology. 2000;56(4):641–646. PMID: 11018622
- Wessells H, Levine N, Hadley ME, Dorr R, Hruby V. Melanocortin receptor agonists, penile erection, and sexual motivation: human studies with Melanotan II. International Journal of Impotence Research. 2000;12 Suppl 4:S74–S79. PMID: 11035391
- Habbema L, Halk AB, Neumann M, Bergman W. Risks of unregulated use of alpha-melanocyte-stimulating hormone analogues: a review. International Journal of Dermatology. 2017;56(10):975–980. PMID: 28266027
- Hjuler KF, Lorentzen HF. Melanoma associated with the use of melanotan-II. Dermatology. 2014;228(1):34–36. PMID: 24355990
- Schulze F, Erdmann H, Hardkop LH, Anemüller W, Rose C, Zillikens D, Fischer TW. Eruptive naevi and darkening of pre-existing naevi 24 h after a single mono-dose injection of melanotan II. European Journal of Dermatology. 2014;24(1):107–109. PMID: 24334249
- Peters B, Hadimeri H, Wahlberg R, Afghahi H. Melanotan II: a possible cause of renal infarction: review of the literature and case report. CEN Case Reports. 2020;9(2):159–161. PMID: 31953620
- Evans-Brown M, Dawson RT, Chandler M, McVeigh J. Use of melanotan I and II in the general population. BMJ. 2009;338:b566. PMID: 19224885
- Langan EA, Nie Z, Rhodes LE. Melanotropic peptides: more than just ‘Barbie drugs’ and ‘sun-tan jabs’? British Journal of Dermatology. 2010;163(3):451–455. PMID: 20545686
- Breindahl T, Evans-Brown M, Hindersson P, McVeigh J, Bellis M, Stensballe A, Kimergård A. Identification and characterization by LC-UV-MS/MS of melanotan II skin-tanning products sold illegally on the Internet. Drug Testing and Analysis. 2015;7(2):164–172. PMID: 24771717
Related compounds
- PT-141: Lab-made peptide (bremelanotide) that acts on the brain, tested for low sexual desire.
- Kisspeptin: Brain signal that starts the puberty and fertility hormone chain, tested in small human trials.
- BPC-157: Lab-made chain of 15 amino acids, tested in animals for blood vessel growth and tissue repair.