Kisspeptin is a small brain protein made from the KISS1 gene. It switches on the hormone chain that controls puberty and fertility. It has been tested in several small human trials, but no agency has approved it as a medicine.
In brief
- It makes the brain release GnRH in pulses. GnRH then tells the pituitary gland to release LH and FSH, which drive the sex hormones.
- Specialist hormone clinics use it as a test to see how well a person's GnRH nerve cells still work.
- It is being tested as a different way to ripen eggs in IVF, with an LH surge closer to the body's own than hCG gives.
What kisspeptin is
Kisspeptin is a natural signal in the brain that starts the hormone chain behind puberty and fertility. It has been tested in people in a number of small trials since 2005, and in mice and monkeys. The FDA has not approved it as a medicine.
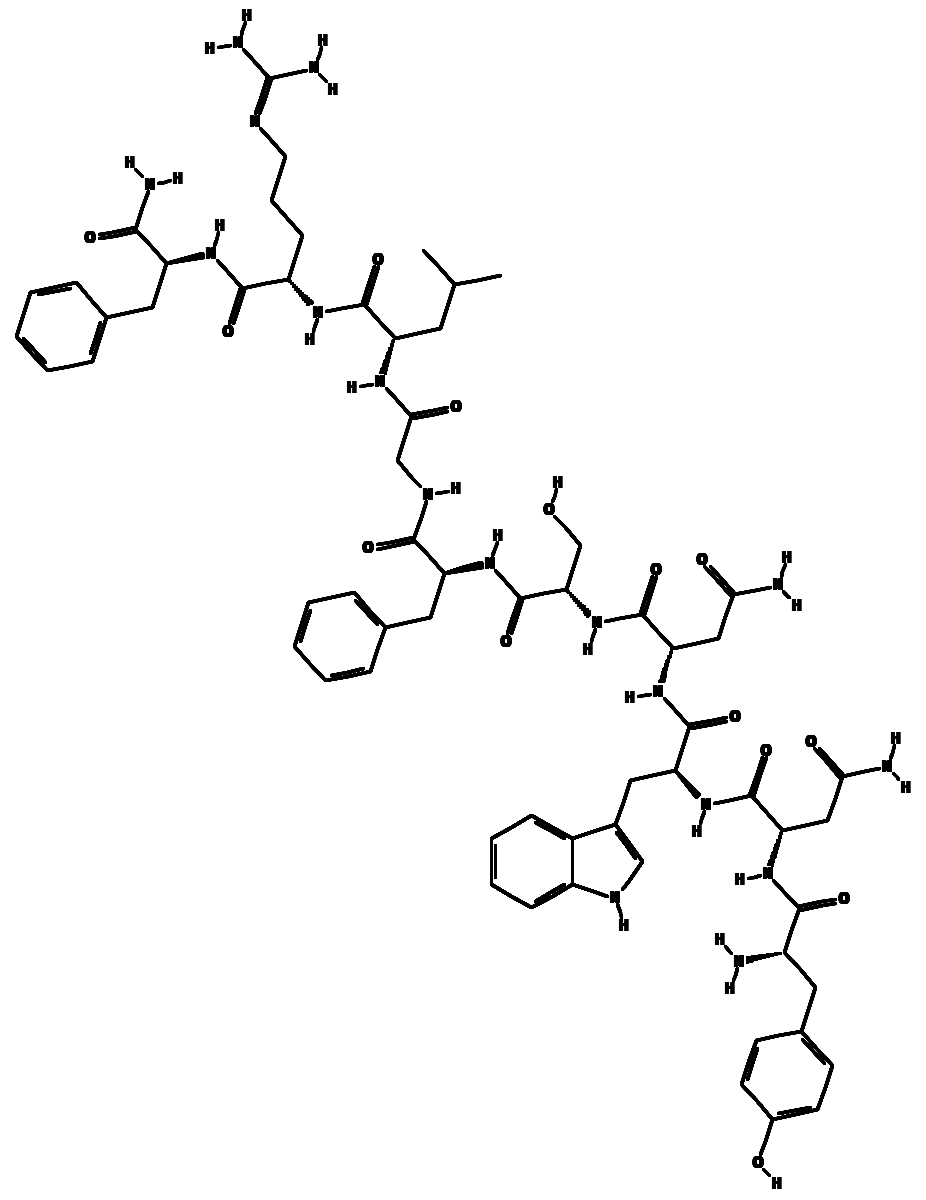
Kisspeptin is a neuropeptide, a short chain of amino acids that nerve cells use as a signal. It comes from a gene called KISS1. The body cuts the gene’s product into several active pieces. Two get the most study:
- Kisspeptin-54, which is 54 amino acids long.
- Kisspeptin-10, a shorter piece made of the last 10 amino acids.
Every form ends in the same 10 amino acids. That shared tail is the part that attaches to the receptor, the docking site on a cell. The receptor is called KISS1R, or GPR54.
Scientists now see kisspeptin as the top switch of the HPG axis. That is the chain of signals running from the hypothalamus (a small region at the base of the brain) to the pituitary gland just below it, and on to the ovaries or testes. Nerve cells that make kisspeptin sit in the hypothalamus, mostly in two spots called the arcuate nucleus and the anteroventral periventricular nucleus. They connect to other nerve cells that make GnRH, short for gonadotropin-releasing hormone, and make them fire in pulses. When the kisspeptin signal is missing, GnRH release fails. Then everything after it fails too: LH (luteinizing hormone), FSH (follicle-stimulating hormone), and the sex hormones made by the ovaries and testes.
This became clear in 2003. Two separate teams found people whose GPR54 gene did not work. Those people had a rare inherited condition in which the body makes too little LH and FSH, with no other known cause. It is called idiopathic hypogonadotropic hypogonadism, and in these families it was passed on in an autosomal recessive way, meaning a faulty copy came from each parent [1], [2]. Within two years, kisspeptin given into a vein had raised LH and FSH in healthy men [3]. That started a line of human research that is still going. The best known group is led by Professor Waljit Dhillo at Imperial College London.
Today a few specialist hormone clinics use kisspeptin as a test of the GnRH system. It is also being studied as a different way to ripen eggs during IVF (in vitro fertilization).
How much research there is
Compared with most research peptides, kisspeptin has more human evidence behind it. That evidence includes human gene studies and several published trials. The trials were small.
| Question | Answer |
|---|---|
| Human gene studies | Settled. Seminara 2003 in NEJM and de Roux 2003 in PNAS |
| First test in people | Dhillo 2005 in JCEM. Kisspeptin-54 into a vein raised LH, FSH and testosterone in healthy men |
| Use as a hormone test | Used for diagnosis in specialist reproductive hormone clinics |
| Egg ripening in IVF | Two Phase 2 randomized trials, Abbara 2015 and Abbara 2017, cover dose finding. An earlier study, Jayasena 2014, reported the first live births |
| Checked by other labs | Yes, by several separate groups: Imperial College London, MGH and Harvard, the Pittsburgh primate lab, and clinics in continental Europe |
Most of the human trial work comes from the Dhillo group at Imperial College London. The Seminara group at Massachusetts General Hospital has added to it. So have separate clinics in continental Europe and Asia.
How it works
Kisspeptin sits very high in the chain. It does not act on the pituitary, the ovaries or the testes directly. It works one step above GnRH and gives the go signal that lets GnRH come out in pulses. There are three parts to the story: the receptor, the GnRH nerve cells, and the hormones that follow.
The GPR54 receptor
GPR54 belongs to a large family called class A G protein-coupled receptors. GnRH nerve cells in the hypothalamus carry a lot of it. When kisspeptin attaches, the main signal runs through a protein called Gαq/11. That turns on an enzyme, phospholipase C. Two messenger molecules, IP3 (inositol trisphosphate) and diacylglycerol, are then made, and calcium rises inside the cell [4]. A second route, MAPK/ERK, adds slower effects on which genes get read.
The receptor is nearly the same across mammals. Its best known job is in the brain’s reproductive hormone system, and that is why scientists see it as a drug target. It is not found only there. It also shows up in ovary and testis tissue, the placenta, and the islet cells of the pancreas. What it does in those places is still being studied.
The key proof that GPR54 is a master switch for reproduction came from the two 2003 gene papers:
- Seminara and colleagues studied a family in which the parents were related by blood. Family members with two copies of a GPR54 mutation had low LH and FSH, with a normal sense of smell [1]. Doctors call this normosmic hypogonadotropic hypogonadism.
- De Roux and colleagues, working at the same time, found a second mutation that stopped the gene from working. The patients had the same condition [2].
Taken as a pair, the papers showed that people need GPR54 signals to start puberty normally and to stay fertile as adults.
Turning on GnRH nerve cells
Nothing known turns on GnRH nerve cells more strongly than kisspeptin. In tests that record the electrical activity of cells, even picomolar amounts, which are extremely tiny, made GnRH nerve cells fire and keep firing.
In 2005, Messager and colleagues put kisspeptin-10 on pieces of mouse hypothalamus kept alive in a dish. GnRH came out. In mice bred without GPR54, nothing happened. So the place where kisspeptin acts is the GnRH nerve cell itself [4].
Two groups of kisspeptin nerve cells take part:
- The arcuate (ARC) group. These cells also make two other signals, neurokinin B and dynorphin, so they are called “KNDy” neurons. Scientists think they set the pulse beat behind steady GnRH release in both sexes.
- The anteroventral periventricular (AVPV) group. This group differs between males and females. In females it drives the LH surge that comes just before ovulation, when rising estrogen pushes the system up instead of holding it back.
The Plant group took this into primates. Kisspeptin-10 caused a strong release of GnRH in young rhesus monkeys, and it could start the puberty system early [5].
Reviews by Navarro pulled the KNDy model together. In that model, a network of cells acts like a clock for GnRH pulses, and kisspeptin is its output. The network first weighs feedback from sex hormones, the body’s energy state, and day length [6].
The hormones that follow
GnRH leaves the hypothalamus through a small set of blood vessels that lead straight to the pituitary. After that the usual HPG pattern plays out:
- GnRH attaches to its receptor on pituitary cells called gonadotrophs. They release LH and FSH.
- LH in males makes Leydig cells in the testes produce testosterone.
- LH in females makes theca cells in the ovary produce androgens and brings on ovulation.
- FSH in males supports the making of sperm.
- FSH in females supports granulosa cells and the growth of egg follicles.
- Sex hormones then signal back to the kisspeptin nerve cells in the hypothalamus and to the pituitary. This controls how much more GnRH is released.
Dhillo and colleagues were the first to show, in 2005, that kisspeptin from outside the body could drive this whole chain in people. Six healthy men got kisspeptin-54 into a vein for 90 minutes at 4 pmol/kg/min. Compared with salt water, their blood LH, FSH and testosterone rose significantly [3]. The later human research in reproductive hormones rests on this first test.
What the studies found
Several peer-reviewed human trials have been run since 2005. The findings are grouped by topic.
Using it as a hormone test
Kisspeptin acts one step above GnRH. So giving a test dose shows whether the GnRH nerve cells themselves are working. A standard test with GnRH, or with a drug that copies GnRH, cannot show that. Specialist clinics use kisspeptin-10 or kisspeptin-54 this way. It helps tell whether low LH and FSH come from the hypothalamus or from the pituitary. It also shows how much the GnRH nerve cells have in reserve.
- First response in people. The 2005 Dhillo study showed that kisspeptin-54 into a vein reliably raises LH, FSH and testosterone in healthy men. Any later use as a test builds on that drug-effect data [3].
- Two kinds of response in late puberty. In 2018, Chan and colleagues gave kisspeptin to teenagers whose puberty was late or had stalled. The results split into two groups. Some teens had a strong LH rise, much like healthy adults. Others had little or none. The authors suggested the split might help predict who has late puberty that will pass without treatment and who has hypogonadotropic hypogonadism from birth [7].
Trials in reproductive hormones
Other studies looked at more than one-time testing, in both sexes.
- One shot under the skin. Hypothalamic amenorrhea is a condition in which periods stop because the hypothalamus sends too little signal. In 2009, Jayasena and colleagues gave women with this condition a single injection of kisspeptin-54 under the skin. LH and FSH went up quickly. So the GnRH system above the pituitary was intact in these women, and a drug could switch it back on [8].
- A 12-hour drip. A later trial gave women with the same condition kisspeptin-54 into a vein for 12 hours. LH pulses came more often. This supports the idea of a treatment drip, which is a different use from a single test dose [9].
- Dose and fading response. Studies with repeated doses also tracked how the response to kisspeptin weakens. Scientists call this desensitization or tachyphylaxis. The results help in choosing doses and drip schedules for studies.
Egg ripening in IVF
IVF is where kisspeptin research has gone furthest toward use in patients. Before eggs are collected, doctors must set off an LH surge so the eggs finish ripening. The usual trigger is hCG (human chorionic gonadotropin) or a drug that copies GnRH. In women who respond strongly, hCG carries a significant risk of ovarian hyperstimulation syndrome, or OHSS. Kisspeptin causes a shorter LH surge that is closer to the body’s own. Scientists have tested it as a safer option.
- Live births. In 2014, Jayasena and colleagues reported on 53 women having IVF. Kisspeptin-54 ripened their eggs, and live births followed. No earlier human study had shown that a kisspeptin trigger could carry IVF through to a full result [11].
- Phase 2 in women at risk of OHSS. In 2015, Abbara and colleagues published the first randomized dose-finding study of kisspeptin-54 as an IVF trigger. It included 60 women at high risk of OHSS. The share of eggs that ripened depended on the dose [10].
- A second dose. In 2017, Abbara and colleagues ran a Phase 2 randomized controlled trial of two doses of kisspeptin-54. Two doses yielded more ripe eggs than one. That helped refine the trigger schedule [12].
Hypogonadotropic hypogonadism
The 2003 gene work tied this condition, HH for short, to a GPR54 that does not work. So kisspeptin matters for these patients. Research has asked two things. Which HH patients still respond to kisspeptin? And can kisspeptin be used as a treatment to bring back the body’s own reproductive function?
- Sorting patients. A kisspeptin test can pick out HH patients whose GnRH nerve cells still work. In theory a drug acting above GnRH could help them. In other patients the GnRH network itself is damaged.
- The first families. The families described by Seminara and de Roux are still the clearest real-life proof that working kisspeptin signals are needed for normal puberty and adult fertility in humans [1], [2].
Puberty problems
Because kisspeptin is central to the start of puberty, it is a natural tool for studying puberty that is late or absent.
- Testing teenagers. In the 2018 Chan study of teens with stalled puberty, the size of the LH rise separated those likely to move forward without help from those unlikely to [7].
- Monkey data. In primates, giving kisspeptin switched on the resting GnRH system of young animals ahead of time. This supports a model in which the timing of puberty is limited by how much kisspeptin is put out, not by how mature the GnRH nerve cells are [5].
- Wider reviews. Reviews fold these results into one model. In it, kisspeptin is the gatekeeper for the start of puberty and for fertility across mammal species [6], [13].
Notes for lab work
The published work points to several things that affect lab results.
- Which form. Kisspeptin-54 and kisspeptin-10 move through the body in ways that overlap but are not the same. Kisspeptin-10 has a short half-life in blood, which suits quick single-dose tests. Kisspeptin-54 acts longer. It is the usual choice for drip studies and trigger studies.
- How it is given. Published human studies have used a drip into a vein, a single dose into a vein, and injection under the skin. The route changes the peak level and how long the LH response lasts.
- Fading response. Steady exposure at high doses dulls the response to kisspeptin. Pulsed or time-limited dosing tends to give LH and FSH rises that repeat more reliably than constant exposure does.
- Sex and cycle phase. The size and shape of the response differ between men and women. In women it also shifts across the menstrual cycle, because estrogen changes how the AVPV kisspeptin nerve cells behave.
- Storage and handling. Freeze-dried kisspeptin is stable at minus 20 °C. Once mixed into liquid it is kept at 2 to 8 °C and used promptly. Research that others can repeat depends on a Certificate of Analysis that confirms what the material is and how pure it is.
Legal status in the US
- Not FDA approved. The FDA has not approved kisspeptin for treating people. Neither has the EMA in Europe or the MHRA in the UK.
- Used in studies only. In the trials cited here, kisspeptin was given under research permissions at specialist clinics. Lab work with it calls for proper oversight by an institution and an ethics board.
Limits of the research
- Small trials. The human studies cited here are small. The first one had six men, and the IVF trials had 53 and 60 women.
- One main group. Most of the trial work comes from a single team at Imperial College London.
- Early stage. The IVF work has reached Phase 2. Use as a test is limited to specialist clinics.
The gene studies and early trials agree that kisspeptin switches on the reproductive hormone chain in people. It is still a research tool and not an approved medicine.
References
Selected peer-reviewed references. Ordered by appearance in this guide.
- Seminara SB, Messager S, Chatzidaki EE, et al. The GPR54 gene as a regulator of puberty. New England Journal of Medicine. 2003;349(17):1614–1627. DOI: 10.1056/NEJMoa035322
- de Roux N, Genin E, Carel J-C, Matsuda F, Chaussain J-L, Milgrom E. Hypogonadotropic hypogonadism due to loss of function of the KiSS1-derived peptide receptor GPR54. Proceedings of the National Academy of Sciences USA. 2003;100(19):10972–10976. DOI: 10.1073/pnas.1834399100
- Dhillo WS, Chaudhri OB, Patterson M, et al. Kisspeptin-54 stimulates the hypothalamic-pituitary gonadal axis in human males. Journal of Clinical Endocrinology & Metabolism. 2005;90(12):6609–6615. DOI: 10.1210/jc.2005-1468
- Messager S, Chatzidaki EE, Ma D, et al. Kisspeptin directly stimulates gonadotropin-releasing hormone release via G protein-coupled receptor 54. Proceedings of the National Academy of Sciences USA. 2005;102(5):1761–1766. DOI: 10.1073/pnas.0409330102
- Shahab M, Mastronardi C, Seminara SB, Crowley WF, Ojeda SR, Plant TM. Increased hypothalamic GPR54 signaling: a potential mechanism for initiation of puberty in primates. Proceedings of the National Academy of Sciences USA. 2005;102(6):2129–2134. DOI: 10.1073/pnas.0409822102
- Navarro VM. New insights into the control of pulsatile GnRH release: the role of Kiss1/neurokinin B neurons. Frontiers in Endocrinology (Lausanne). 2012;3:48. DOI: 10.3389/fendo.2012.00048
- Chan YM, Lippincott MF, Kusa TO, Seminara SB. Divergent responses to kisspeptin in children with delayed puberty. JCI Insight. 2018;3(8):e99109. DOI: 10.1172/jci.insight.99109
- Jayasena CN, Nijher GMK, Chaudhri OB, et al. Subcutaneous injection of kisspeptin-54 acutely stimulates gonadotropin secretion in women with hypothalamic amenorrhea. Journal of Clinical Endocrinology & Metabolism. 2009;94(11):4315–4323. DOI: 10.1210/jc.2009-0406
- Jayasena CN, Abbara A, Veldhuis JD, et al. Increasing LH pulsatility in women with hypothalamic amenorrhea using intravenous infusion of kisspeptin-54. Journal of Clinical Endocrinology & Metabolism. 2014;99(6):E953–E961. DOI: 10.1210/jc.2013-1569
- Abbara A, Jayasena CN, Christopoulos G, et al. Efficacy of kisspeptin-54 to trigger oocyte maturation in women at high risk of ovarian hyperstimulation syndrome (OHSS) during in vitro fertilization (IVF) therapy. Journal of Clinical Endocrinology & Metabolism. 2015;100(9):3322–3331. DOI: 10.1210/jc.2015-2332
- Jayasena CN, Abbara A, Comninos AN, et al. Kisspeptin-54 triggers egg maturation in women undergoing in vitro fertilization. Journal of Clinical Investigation. 2014;124(8):3667–3677. DOI: 10.1172/JCI75730
- Abbara A, Clarke S, Islam R, et al. A second dose of kisspeptin-54 improves oocyte maturation in women at high risk of ovarian hyperstimulation syndrome: a Phase 2 randomized controlled trial. Human Reproduction. 2017;32(9):1915–1924. DOI: 10.1093/humrep/dex253
- Abbara A, Clarke SA, Dhillo WS. Clinical potential of kisspeptin in reproductive health. Trends in Molecular Medicine. 2021;27(8):807–823. DOI: 10.1016/j.molmed.2021.05.008
Related compounds
- Thymosin Alpha-1: Immune peptide from the thymus, sold as an approved drug in many countries.
- PT-141: Lab-made peptide (bremelanotide) that acts on the brain, tested for low sexual desire.
- Melanotan 2: Lab-made copy of a skin-darkening hormone. Never approved, with reports of harm in users.